A 20-year-old male was at a party where, after dancing, he ate a lot of cake because it was “delicious”. After 2-3 hours, he developed a sudden onset of weakness in all 4 limbs. He has had two similar episodes before. He was rushed to the nearest ER. On examination: P: 88/min, BP: 140/96 mm Hg, Pallor+, no thyroid enlargement. He is alert and oriented. No cranial nerve involvement or neck muscle weakness. Motor power is grade 2-3 in all extremities, reflexes sluggish to absent. Sensory exam is normal. Laboratory results reveal the following:
pH 7.4
pCO2 40 mm Hg
PaO2 98 mm Hg
HCO3 24 mEq/L
O2 saturation 98%
Na 140 mEq/L
K 2.2 mEq/L
Cl 103 mEq/
BUN 10 mg/dl
S.Cr 0.8 mg%
S. Ca 10.2 mg/dl
PO4 2.5 mg/dl
Mg 2.2 mg/dl
Urine Electrolytes
Urine Na 100 mEq/L
Urine K 15 mEq/L
Which of the following is the MOST likely diagnosis?
|
|
A. Familial periodic paralysis. |
| B. Renal tubular acidosis | |
| C. Primary hyperaldosternism. | |
| D. Thyrotoxic periodic paralysis |
|
|
Copyright © ABIM Exam World
Created On: 09/12/2017
Last Modified: 10/17/2026
A 35-year-old Caucasian male presents with persistent swelling of both legs associated with dark colored urine for two months. He went to an emergency room 2 months ago for these complaints and was told that he has some protein and blood in the urine. He was treated with levofloxacin for 3 days. There is no other past medical history. No history of skin rash or joint swelling. On examination,n the blood pressure was 130/85 mm H,g and there was bilateral 1+ pedal edema. The rest of the physical examination was normal. Urine analysis showed 3+ proteinuria, 10-15 RBCs per high-power field, and occasional RBC casts. BUN was 10 mg/dL, and serum creatinine was 0.9 mg/dL. Antistreptolysin was negative; C3 was decreased, and C4 was normal. Antinuclear antibodies, ANCA, hepatitis B and C serology were negative. 24-hour urine collection showed 2 g proteinuria, and a kidney biopsy was performed. Light microscopy showed increased mesangial matrix and cellularity, and the glomerular basement membrane appeared irregularly thickened. Silver stain revealed duplication of the glomerular basement membrane in multiple glomeruli. Immunofluorescence showed positive staining for C3, but negative for IgG, IgM and IgA. Electron microscopy revealed electron-dense deposits in the mesangium and subendothelial area.
What is the most likely diagnosis?
| A. Acute poststreptococcal glomerular nephritis | |
| B. Diffuse proliferative lupus nephritis | |
| C. Dense deposit disease | |
|
|
D. C3 glomerulopathy |
| E. |
|
|
Copyright © ABIM Exam World
Created On: 09/12/2017
Last Modified: 10/17/2026
A 25-year-old male comes to the physician complaining of flank pain and hematuria. He says the pain is constant and dull. There is no frequency, urgency or dysuria. He has a history of mental retardation and seizures. On physical exam, his blood pressure is 140/90 mm Hg, and his pulse is 80 bpm. He has multiple yellow papules on his nose and cheeks and numerous blanched skin spots on his face. A 2-3 cm hypopigmented macule is noted on the right arm. CT scan of the head was done as the patient presented with seizures. CT head was reported normal. CT scan of the abdomen shows bilateral hypodense, fat-containing renal masses and cysts.
What is the MOST likely diagnosis associated with these findings?
| A. Von Hippel Lindau | |
| B. Sturge Weber Syndrome | |
|
|
C. Tuberous Sclerosis |
| D. Osler Weber Rendu | |
| E. Neurofibromatosis type 2 |
|
|
Copyright © ABIM Exam World
Created On: 09/13/2017
Last Modified: 10/17/2026
A 15-year-old boy is brought to the ER by his foster mother, who states that when she got home from work, she noticed he was acting very strange. He had slurred speech and seemed confused. He appeared very uncoordinated, and she was unsure whether he fell or hit his head. She states that he is somewhat of a troubled boy but doesn’t know much about his history, as he has been in and out of the foster care system out of state. On physical exam, he is tachycardic and has tachypnoea. Pupils are dilated, but there is no nystagmus.Fundoscopic exam shows optic disc hyperemia. He is relatively uncooperative but not aggressive or hostile. When asked about suicidal thoughts, he responds only with inaudible mumbling. His foster mother left for work 10 hours prior and assumed he left for school. She is unsure when these symptoms began or what may have triggered them. P is 105/ min, BP is 140/90 mm Hg, RR is 28/min, and T is 97.1 F. Laboratory examination is as follows:
Na 135 mEq/L
K 5.0 mEq/L
CL 105 mEq/L
BUN 19 mg/dL
Cr 1.3 mg/dL
HCO3 8 mEq/L
Glucose 100 mg/dL
pH 7.3
pO2 90 mmHg
pCO2 22 mmHg
Measured serum osmolarity: 320 mmol/L
What is the next step in management?
| A. Gastric lavage | |
| B. N-acetylcystiene and activated charcoal | |
| C. Fomepizole | |
|
|
D. Fomepizole and Hemodialysis |
|
|
E. Obtain serum levels of salycylate, methanol and ethylene glycol levels |
|
|
Copyright © ABIM Exam World
Created On: 09/13/2017
Last Modified: 10/17/2026
All of the following help predict AV Graft stenosis EXCEPT:
|
|
A. Hyperpulsatility of the AV Graft |
| B. Ruduced pulse augmentation | |
| C. Increased bleeding and clots | |
| D. Decreased KT/V | |
| E. Decreased Blood Flow rate | |
|
|
F. Surveillance of the graft |
|
|
Copyright © ABIM Exam World
Created On: 09/14/2017
Last Modified: 10/17/2026
A 40-year-old pleasant African man with ESRD secondary to FSGS started automated peritoneal dialysis. His prescription includes 2.5 L and 3 exchanges over 8 hours at night, with a last fill of 2 L. His urine output is 1000 mL/day. A typical ultrafiltration on the cycler is 1000 mL. The average drain volume during the day dwell was 1500 mL before going on the cycler at night.
He came with complaints of lower abdominal wall edema extending to the scrotum over the past 5 days. Without any change in the dialysis prescription, his drain volume before going on the cycler dropped to 900 mL, and the ultrafiltration volume on the cycler came down to 100 mL. He reports no pain with fill or drain.
What is the next step?
| A. Chest X ray PA and lateral view | |
| B. Drain the fluid middle of the day to reduce the dwell time | |
| C. PD catheter manipulation | |
|
|
D. Abdominal CT scan with contrast in the dialysate |
| E. Switch to hemodialysis | |
| F. Pleurodesis |
|
|
Copyright © ABIM Exam World
Created On: 09/14/2017
Last Modified: 10/17/2026
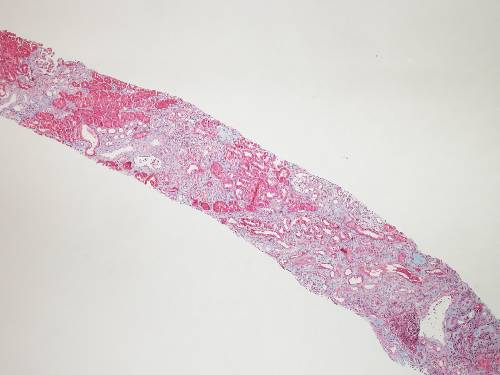
Cyclosporine nephrotoxicity in a renal transplant recipient is associated with all of the following renal biopsy findings EXCEPT:
(THIS PICTURE BELOW IN LOW POWER SHOWS ONE OF THE CLASSICAL FINDINGS IN CSA TOXICITY)

| A. Interstitial Fibrosis | |
| B. Tubular atrophy | |
| C. Endothelial cell swelling | |
|
|
D. Glomerular thrombin deposits |
| E. Glomerular basement membrane thickening | |
|
|
F. Double contours of the GB |
|
|

Copyright © ABIM Exam World
Created On: 09/14/2017
Last Modified: 10/17/2026
A 68-year-old African American male with a known history of diabetes mellitus, hyperlipidemia, CVD, and GERD presents to the ER with chest pain and shortness of breath. The patient says the pain is crushing and radiates to his left arm. It woke him from sleep 30 minutes ago. He took his antacids and 4 tablets of nitroglycerin, and the pain got better. His current medications include low-dose aspirin, metoprolol, glyburide, pioglitazone, lisinopril, simvastatin, and omeprazole. He recently suffered an upper respiratory infection for which he was given Levofloxacin. Vitals: BP 160/95 mm Hg, T 98.1, HR 110. He has no leg edema and no jugular venous distention. EKG shows LVH by voltage criteria with an isoelectric ST segment. Serial troponin levels are normal. A stress test showed evidence of stress-induced ischemia in the anterior leads. He is scheduled for cardiac catheterization the next day. Laboratory results are as follows:
Serum Chemistry:
Na 143 mEq/L
K 3.5 mEq/L
Cl 101 mEq/L
HCO3 22 mEq/L
BUN 35 mg/dL
Cr 3.0 mg/dL
Glucose 110 mg/dL
What would you do to PROTECT the kidneys before doing the cardiac catheterization?
| A. Dopamine IV infusion before and after the procedure. | |
| B. Nifedipine. | |
|
|
C. Isotonic sodium bicarbonate infusion before and after the procedure. |
| D. N Acetyl Cysteine before and after the procedure | |
| E. Start mannitol IV before the procedure | |
| F. Left ventriculogram quickly with coronary angiogram |
|
|
Copyright © ABIM Exam World
Created On: 09/14/2017
Last Modified: 10/17/2026
As per the JNC VIII committee recommendation, for individuals who are part of the African American population, including those with diabetes, the initial treatment should include a thiazide-type diuretic or calcium channel blocker (CCB).
Which of the following thiazide-type diuretics is preferred as the initial antihypertensive therapy?
| A. Hydrochlorthiazide | |
|
|
B. Chlorthalidone |
| C. Indapamide | |
| D. Metalazone | |
| E. Polythiazide |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/16/2026
Which of the following antihypertensive medications resulted in better blood pressure control and cardiovascular outcomes when combined with an ACE inhibitor?
| A. Beta blocker | |
|
|
B. Calcium channel blocker |
| C. Angiotensin Receptor Blocker | |
| D. Diuretics |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/16/2026
The ACCOMPLISH trial is the first major trial addressing the issue of combination therapy in 11,506 patients who were at high cardiovascular risk. The goal blood pressure was <130/80 mm Hg in patients with diabetes or impaired renal function, and <140/90 mm Hg in patients with prior cardiovascular disease.
Which of the following combinations of blood pressure medications was the best in reducing cardiovascular events and slowing the progression of nephropathy in patients with hypertension who were at high risk for such events?
| A. ACEI + Diuretics | |
|
|
B. ACEI + CCB |
| C. ACEI + Beta-blocker | |
| D. CCB + Beta-blocker |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/16/2026
An 18-year-old male is brought to the renal clinic for evaluation of hypertension. There is no history of edema of the feet, puffiness of the face, hematuria, oliguria or recurrent urinary tract infections. He is an active football player, but lately he complains of weakness and muscle cramps. His blood pressure for the last 3-4 years has always been borderline high and during this visit was as noted below.
Physical examination shows: Pulse 100/min; all peripheral pulses are well felt. BP 150/100 mm Hg, Temp. 37.4 degrees C. He is pale. His growth is stunted. His cognitive function is normal, and no focal neurological deficits are noted. Other systems are unremarkable. Laboratory examination is as follows:
Hemoglobin 13.5 g/dL
Hematocrit 42%
Platelet Count 150,000 mm3
White Blood Cells 8,000 mm3
Urinalysis:
Protein 100 mg/24 h
Glucose None
Red Blood Cells None
White Blood Cells None
Leukocyte Esterase Negative
Nitrites Negative
Chemistry:
BUN 13.5 mg/dL
Creatinine 0.9 mg/dL
Sodium 140 mEq/L
Potassium 5.8 mEq/L
Bicarbonate 18.5 mEq/L
Chloride 112 mEq/l
Calcium 9.2 mEq/L
Phosphorus 3.2 mg/dL
Aldosterone 5 ng/mL
PRA <1.0 ng/dL/hr
Glucose 100 mg/dL
HbA1C 5.30%
S. Osmolality 282 mOsmol
Uric Acid 5.3 mg/dL
ESR 9.8 mm/h
ABG:
pH 7.25
PCO2 32 mm Hg
HCO3 16 mEq/L
PO2 90 mm Hg
USG: Normal-sized kidneys, no hydronephrosis
Considering the history and the laboratory findings, which of the following is most likely the cause of hypertension in this patient?
| A. Liddle's Syndrome | |
|
|
B. Gordon's Syndrome |
| C. Congenital adrenal hyperplasia | |
| D. Glucocorticoid-remediable aldosteronism | |
| E. Mineralocorticoid receptor activating mutation |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/16/2026
A 56-year-old male was brought to the emergency room with drowsiness and lethargy. He has had these symptoms for the past 2 days. He complains of a recent history of anorexia, nausea, and vomiting. He has diabetes mellitus and has been on glimepiride 1 mg daily for the last 4 years. One week ago, he had decreased vision with redness in his right eye. He was treated by his ophthalmologist with drops,s which seem to have resolved the problem. He currently takes cholecalciferol weekly for osteoporosis. On physical examination, his pulse is 80/min, blood pressure is 140/90 mm Hg, respiratory rate is 20/min, and temperature is 97.7°F. The patient appears drowsy but shows no focal neurological deficits. Review of systems is otherwise unremarkable. Urinalysis is positive for glucose and negative for proteinuria, WBCs, and RBC casts. A 24-hour urinary protein collection shows proteinuria of 3.5 g/day. Further labs reveal:
Hemoglobin 8 gm%
Hct 24%
MCV 85
WBC 7800/ml
PMN 80%
Lymphocytes 20%
ESR 80 mm/hr
Na 145 mEq/L
BUN 80 mg/dL
Cr 1.8 mg/dL
CL 115 mEq/L
HCO3 25 mEq/L
Uric acid 5.8 mg/dL
Ca 14 mg/dl
PO4 2.8 mg/dL
Total Protein 7.8 gm/dL
Albumin 3.5 mg/dL.
Vitamin D 40 ng/ml
PTH 10 pg/ml
Which of the following is most likely the cause of his hypercalcemia?
| A. Vitamin D toxicity | |
| B. Primary hyperparathyroidism | |
|
|
C. Multiple myeloma. |
| D. Sarcoidosis |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
A 25-year-old female is referred by her primary care provider for evaluation of hypertension and hypokalemia. Her primary care provider has already started her on oral potassium; despite this, her potassium remains low. Despite amlodipine and lisinopril, her blood pressure is 154/96 mm Hg. There is no renal bruit. Systemic and fundus examinations are normal. Her mother was also diagnosed with hypertension at an early age. Her brother died of a cerebrovascular accident 2 years ago. Laboratory findings are as follows:
Na 140
Potassium 2.8
Chloride 100
HCO3 26
BUN 15
Creatinine 0.8
Glucose 110
TSH and Cortisol are normal
ACTH elevated
Renin 0.7 (Low)
Aldosterone 48 (elevated)
Urinalysis:
Sodium 240 mEq/D
Potassium 98 mEq/D
Urinary 18-OH Cortisol and 18-oxocortisol are elevated.
The most appropriate treatment for this patient is:
| A. Steroids | |
| B. Spironolactone | |
|
|
C. Steroids + Spironolactone |
| D. Amiloride |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
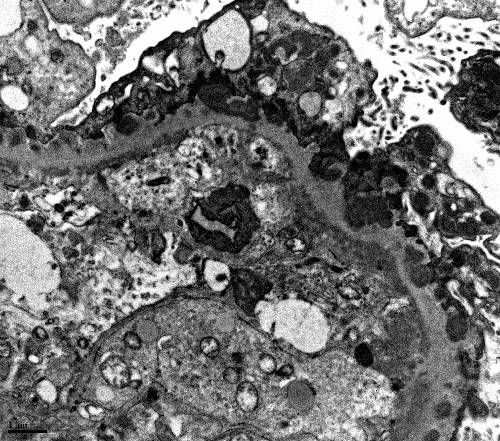
A 60-year-old with recently diagnosed colon cancer and diabetes presents with bilateral pedal edema; BP is 120/80 mm Hg. Urinalysis showed 4+ protein, no RBCs or WBCs, and 8-10 Hyaline casts. His BUN is 20, Creatinine is 1 mg/dL, and albumin is 2 grams/dL. A 24-hour urine collection showed 10 grams of protein. The patient undergoes a kidney biopsy. The EM is shown below :

What is the most likely diagnosis?
| A. Crescentic GN | |
| B. IgA nephropathy | |
| C. Minimal change disease | |
| D. Focal segmental glomeruloscerosis | |
|
|
E. Membranous nephropathy |
| F. Diabetic nephropathy |
|
|
The correct answer is E
Membranous Nephropathy.
Electron microscopy shows subepithelial electron-dense deposits, as classically seen in membranous nephropathy. If in the question there is a suggestion of colon, breast, or lung cancer, then the glomerulopathy is usually membranous. Therefore, histopathological findings support the diagnosis: subepithelial electron-dense deposits.
Explanation:
BOARD POINT - FAMILIARIZE YOURSELF WITH THESE ASSOCIATIONS :
1. Solid cancers (colon, breast, lung, renal) plus proteinuria = Membranous nephropathy
2. Hodgkin's lymphoma plus proteinuria = Minimal change disease
3. HIV plus proteinuria = Focal segment glomerulosclerosis FSGS
4. Pamidronate plus protenuria = FSGS (rare)
5. Myeloma, no albuminuria on dipstick, but proteinuria on protein/creatinine ratio in 24-hour urine: Light chain nephropathy
6. Myeloma th with nonspecific proteinuria (dipstick, urine protein/creatinine ratio in 24-hour urine): Light chain nephropathy or amyloidosis.
BOARD POINT - FAMILIARIZE YOURSELF WITH THESE HISTOPATHOLOGY ASSOCIATIONS FOR VARIOUS GLOMERULAR DISEASES
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
You are the nephrologist on call. The ER calls you for an 18-year-old female who is complaining of vomiting and diarrhea. Her serum sodium is 116 mEq/L and Serum potassium is 5.9 mEq/L. On physical examination, the patient is drowsy; pulse 126/min, BP 90/60 mm Hg, and RR 32/min. Her chest is clear. Her heart sounds are normal, with no murmur. The patient is drowsy but arousable, with no focal neurological deficit. Laboratory findings are as follows:
Hb 16 gm/dl
WBC 12,800/cmm
Polymorph 46%
Lymphocytes 16%
Eosinophils 4%
Monocytes 4%
Platelets 2,40,000/cmm.
CL 70 mEq/L
BUN 10 mg/dl
Creatinine 0.5 mg/dl
Na 116 mEq/L
K 5.8 mEq/L
Urinalysis:
pH 6.4
Protein trace
Glucose absent
Microscopic: occasional WBCs & RBCs
Urinary Na 90 mEq/L
Urinary K 20 mEq/L
ABG
PH 7.32
PCO2 36
HCO3 20 mEq/L
PaO2 92
O2 saturation 98%
S. Cortisol 6.00 mg/dl
TSH 3.5 IU/m (Normal 0-5 IU/m ).
Both plasma Renin and Aldosterone are high.
Which of the following conditions is most likely with these findings?
|
|
A. Type 4 RTA |
|
|
B. Pseudo-hypo-aldosteronism Type 1 |
| C. Gordon's syndrome | |
| D. Diarrhea |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
A 32-year-old male is brought to the renal clinic with a history of hematuria, oedema of the feet, and puffiness of the face. He reports fever and sore throat a week ago. He also complains of breathlessness on exertion and oliguria. Physical examination shows: Pulse 100/min, BP 150/100 mm Hg, and Temp. 37.4 C. He is pale. He has facial puffiness and oedema of the feet. Systemic examination-unremarkable. Laboratory examination is as follows:
Hb 10.5 g/d
Hct 34%
Platelet 250,000 mm3
WBC 8,000 mm3
Differential count: P 80% L 12% E 6% M 2%
ESR 9.8 mm/h
Urinalysis:
Protein 3000 mg/24 h
Glucose None
RBC 50-60/hpf Dysmorphic
WBC occasional
Leukocyte Esterase Negative
Nitrites Negative
BUN 40 mg/dL
Creatinine 3.9 mg/dL
Sodium 140 mEq/L
Potassium 4.2 mEq/L
Bicarbonate 25.5 mEq/L
S. protein 5.5 g/dl
S. Albumin 2.5 g/dl
Calcium 9.2 mEq/L
Phosphorus 3.2 mg/dL
Glucose 100 mg/dL
Uric Acid 5.3 mg/dL
C 3 Low
C4 normal
HBsAg /HIV Neg
ANA Neg
Kidney Biopsy: Shows enlarged Glomeruli, lobular accentuation, mesangial hypercellularity, endo-capillary proliferation and double contour along the capillary wall. IF shows bright C3 in the mesangium and capillary wall with absent immunoglobulin staining.
Electron Microscopy: Suggestive of dense deposits.
What is the BEST treatment option for this patient?
| A. Plasma exchange + Rituximab | |
| B. Rituximab | |
|
|
C. Eculuzimab |
| D. Cyclophosphamide + Steroids |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
A 36-year-old female was diagnosed with membranous nephropathy secondary to SLE. Her 24-hour protein excretion was 7.5 gms/day. Her serum creatinine was 0.9mg/dl. She was started on 500 mg of cyclophosphamide IV every 15 days (Euro-Lupus) and prednisolone 1 mg/kg orally per day. After 3 months of therapy, she presented with decreased urine output, puffiness of the face, and oedema of the feet. On physical examination, her temperature was 37°C, blood pressure was 160/100 mm Hg, pulse was 90/min, and respiratory rate was 20/min. She is anemic, with facial puffiness and foot oedema. On systemic examination, air entry was decreased at the bases of both lung fields, and heart sounds were distant and feeble. Chest X-Ray reveals bilateral pleural effusions. Echocardiogram reveals mild to moderate pericardial effusion. Laboratory examination is as follows:
Hemoglobin 10.0 g/dL
Hematocrit 34%
Platelet Count 150,000 mm3
WBC 8,000 mm3
Differential count: T P 80% L 12% E 6% M 2%
ESR 50.8 mm/h
Urinalysis:
Protein 1450 mg/24 h
Glucose None
RBCs 70-80/HPF dysmorphic
WBCs 5-8/HPF
Leukocyte Esterase Negative
Nitrites Negative
BUN 35 mg/dL
Creatinine 3.9 mg/dL
Sodium 140 mEq/L
Potassium 5.2 mEq/L
Bicarbonate 15.5 mEq/L
Calcium 9.2 mEq/L
Phosphorus 5.6 mg/dL
Glucose 100 mg/dL
Uric Acid 5.3 mg/dL
C3 & C4 decreased
ANA positive
dsDNA positive
Repeat biopsy shows:

Which of the following is the most appropriate therapy for her current condition?
| A. Mycophenolate and steroid | |
|
|
B. Mycophenolate, tacrolimus and steroids |
| C. Rituximab | |
| D. I.V Immunoglobulins | |
| E. Plasma exchange |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
A 30-year-old man comes to your office for a painful rash on the neck. He has fever and malaise. He has a history of HIV. He is currently taking Tenofovir, emtricitabine, and indinavir. The rash is suggestive of Herpes Zoster rash :
Physical examination reveals no oral cavity lesions. His cu rent CD4 count is 250/mm3. Hischemistry iss normal. He is started on an intravenous medication for his rash. Two days later, his chemistry is as follows:
Na 135 mEq/L
K 4.5 mEq/L
CL 100 mEq/L
HCO3 24 mEq/L
BUN 21 mg/dL
Cr 2.0 mEq/L
Glucose 95 mg/dL
Calcium 9.4 mg/dl
Urinalysis shows needle-shaped crystals in the sediment.
Which of the following is most likely the cause of his renal problem?
| A. Indinavir | |
| B. Tumor lysis syndrome | |
| C. Antifreeze ingestion | |
|
|
D. Acyclovir |
| E. IV TMP/SMX |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
In patients with CKD and ESRD, Vitamin D appears to protect against cardiovascular events by controlling secondary hyperparathyroidism. The OPERA trial evaluated the effect of the Vitamin D analog paricalcitol in CKD stages 3-5 with left ventricular hypertrophy. The study observed the effect on left ventricular mass and function.
Which of the following statements is true about the effect of paricalcitol in CKD and ESRD patients?
| A. Paricalcitol treatment reduced LV mass | |
| B. Paricalcitol treatment preserved LV ejection fraction | |
| C. Paricalcitol treatment improved pulse wave velocity and arterial stiffness | |
| D. Paricalcitol treatment improved blood pressure control | |
|
|
E. Paricalcitol treatment significantly reduced PTH and alkaline phosphatase |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
You are rounding on your patients in the dialysis unit and see a 65-year-old gentleman with ESRD due to chronic interstitial disease. He also has a history of diet-controlled diabetes mellitus and hypertension. His other past medical history is significant for dyslipidemia, coronary artery disease, hypothyroidism, gout and depression. He has been hospitalized in the recent past for swelling and pain of his right great toe. He was seen by the foot doctor, a scan was done, and eventually the great toe had to be amputated. H has been on hemodialysis 3 times a week. His weekly Kt/V is 1.9. You are conducting the monthly blood work review for this patient. You note that his hemoglobin has been persistently low for the past few monthly blood draws. He is currently on 100 mcg of Darbepoetin weekly on dialysis. On enquiry, there is no history of blood loss in the form of hematemesis, melena, hematochezia or hemoptysis. His active medications include losartan, Atorvastatin, Calcitriol, multivitamin supplements, paroxetine, allopurinol and aspirin.
His pertinent blood work is as follows:
Test | Result |
WBC | 4500 cells /cumm |
Hemoglobin | 8.2 g/dL |
Platelet count | 450 thousand /cumm |
Reticulocyte count | Normal |
Iron | 55 (range 50-150) |
Total iron-binding capacity | 250 g/dl (range 250-310) |
Transferrin saturation | 20% |
Ferritin | 1400 ng/ml (range 20-235) |
Haptoglobin | 400 mg/dl (range 83-267) |
Lactate dehydrogenase | 240 U/L (range 80-225) |
Total bilirubin | 1.0 mg/dl |
Folate | 7 ng/ml (range 1.8-9.0) |
B12 | 500 pg/ml (range 200-800) |
Peripheral blood smear. | Normal RBC morphology, few burr cells. |
Which of the following is true about this patient’s anemia?
Omitted
|
Correct Answer: Option C: This patient has chronic inflammation, which contributes to his anemia.
Explanation:
10-15% of patients receiving erythrocyte-stimulating agents (ESAs) develop resistance. There are multiple reasons why ESRD patients develop resistance.
ESA resistance occurs due to the following reasons:
Iron deficiency.
Chronic inflammation.
Under-dialysis.
Hemolysis.
Folate and B12 deficiency.
Chronic blood loss.
Anti-EPO antibodies.
Pure red cell aplasia.
Failed chronic renal allograft.
ACEI/ARB.
Aluminum overload.
Hyperparathyroidism.
Hematological disorders or malignancy.
Option A: Incorrect option. ESRD is associated with erythropoietin deficiency—the patient has already been initiated on ESA. There is no need to measure EPO levels. There is no evidence that measuring EPO levels is part of anemia management in aKD.
Option B: Incorrect option. ESRD is an inflamed state. In an inflammatory milieu, hepcidin production increases. The hepatic iron-regulatory hormone Hepcidin and its receptor, the cellular iron exporter ferroportin, form a feedback-regulated mechanism that maintains iron-transferrin concentrations, erythropoiesis and other functions, ensuring sufficient iron availability and preventing toxicity. In chronic kidney disease, inflammation and impaired renal clearance increase plasma hepcidin, inhibiting duodenal iron absorption and sequestering iron in macrophages. Hepcidin can cause systemic iron deficiency, reduced iron availability for erythropoiesis, and resistance to endogenous and exogenous erythropoietin.
Choice C: Correct option. Refer to explanation for option B. He had swelling in the great toe; a foot doctor saw him, a bone scan was done, and subsequently the amputation: all suggestive of an infective etiology, probably osteomyelitis. There is a temporal relationship between the patient’s symptoms and underlying chronic inflammatory state.
The high ferritin also suggests an inflammatory state.
Choice D: Incorrect option. Pure red cell aplasia, a form of severe ESA hyporesponsiveness mediated by anti-erythropoietin antibodies, was first reported with certain formulations of Epoetin alfa but has now been reported with all commercially available forms of ESA. This syndrome presents with rapid-onset severe anemia (hemoglobin <7 g/dL), severe reticulocytopenia (reticulocyte count <10,000/? L), and marked elevations in serum ferritin (>1000 ng/mL) and transferrin saturation (>70%) due to low iron utilization. Pure red cell aplasia is unlikely given the absence of characteristic laboratory findings. Moreover, the patient did ot receive Epoetin alfa.
Choice E: Incorrect option. Under-dialysis leads to anemia due to the same mechanism mentioned earlier in option B. Under-dialysis worsens the uremic milieu, which in turn leads to an inflammatory state. This leads to anemia. The patient in this clinic vignette has been dialysed appropriately. His weekly Kt/V is 1.9, which is above the target goal of 1.7
Copyright © ABIM Exam World
Created On: 10/22/2018
Last Modified: 10/16/2026
50-year-old female patient whose group B is being evaluated for kidney transplant surgery. She had ESRD secondary to analgesic nephropathy and has been on hemodialysis for the last 5 years. She has had multiple sensitization events in the form of 3 pregnancies and several blood transfusions. Her current calculated PRA against class I antigen is 97% and against class II antigen is 99%. She has been enrolled in the national highly sensitized recipient program.
Her husband, who is blood group matched, came forward as a potential kidney donor, but she had a positive Flow B and T-cell crossmatch against him. Single antigen bead assay demonstrated donor-specific antibodies against class II across DQB*15 and DPB*14. This transplant did not materialize as the patient declined the desensitization protocol. Now her younger brother comes forward as a potential donor. He is blood group A, and the flow B and T-cell crossmatch is negative, with no demonstrable donor-specific antibodies against this donor. The patient wants to know more about ABO-incompatible transplant.
Which of the following statements about the ABO incompatible transplant is correct?
| A. Three-year graft survival is inferior to blood group compatible transplants. | |
| B. The infectious and bleeding complications post ABOI kidney transplant are the same as blood matched kidney transplant. | |
|
|
C. All patients undergoing ABOI transplant need to undergo desensitization using IVIg, Plasma exchange, Rituximab irrespective of their donor/recipient pair Anti ABO titers for optimal outcomes. |
|
|
D. C4d staining on protocol biopsies is common feature and does not necessarily mean an antibody mediated rejection process in the absence of allograft dysfunction. |
|
|
Correct answer: Option D: C4d staining on protocol biopsies is a common feature and does not necessarily mean an antibody-mediated rejection process.
Explanation:
Choice A: Three-year graft survival is inferior to blood group-compatible transplants is incorrect. A comprehensive database analysis of 1420 ABOI living donor (LD) kidney transplants performed in 101 centers from 2005 to 2012 compared graft and patient survival with a matched cohort of ABO-compatible transplant recipients. Three-year graft and patient survival were ultimately identical. 1
Choice B: The infectious and bleeding complications post ABOI kidney transplant are the same as in blood-matched kidney transplant is also incorrect. Using USRDS and Medicare data from 2000–2007, 119 ABOI (non-A2 donor) transplant recipients were identified. Compared with ABO-compatible recipients, the risks of infectious and hemorrhagic complications were significantly higher, with a 2.2-fold higher risk of pneumonia, a 3.5-fold higher risk of wound infections, a 56% higher risk of pyelonephritis, and a nearly 2- fold higher risk of hemorrhage 2
Choice C: All patients undergoing ABOI transplant need to undergo desensitization using IVIg, Plasma exchange, Rituximab irrespective of their donor/recipient pair. Anti-ABO titers for optimal outcomes is also an incorrect answer. Historically, ABOI transplantation has been successful when performed after desensitization with plasmapheresis, intravenous Ig (IVIG), rituximab, and/or splenectomy to achieve ABO IgG antibody titersof 1:4. A recent publication demonstrated that these intensified treatments might not be necessary in donor/recipient pairs who have low-to-moderate titer ABO incompatibility 3
Choice D: C4d staining on protocol biopsies is a common feature and does not necessarily mean an antibody-mediated rejection process; in the absence of allograft dysfunction, this is the correct answer. C4d staining is not an uncommon feature seen in the protocol biopsies done in ABOI kidney transplant recipients. In the absence of allograft dysfunction, C4d staining has no clinical relevance and is part of graft accommodation.
Copyright © ABIM Exam World
Created On: 10/30/2018
Last Modified: 10/16/2026
A 28-year-old Caucasian gentleman comes to the clinic for a follow-up visit. He has been found to have type 1 diabetes mellitus since the age of 12. His cousin has the same disease. He reports no symptoms. He has been using an insulin pump with insulin aspart. He monitors blood sugar with a flash glucose monitor and uses carbohydrate counting for boluses. He reports infrequent hypoglycemic episodes, particularly 2 hours post-lunch, but manages by himself. He exercises at least60 minutes per day. His vitals show BP of 118/6 mHg. His BMI is 23.2. System examination is unremarkable.
His laboratory investigations are reported as follows.
Characteristic | Value |
Hemoglobin | 14.2 gm/L |
WBC count | 6.8 X 10³/cubic mm |
Platelet count | 241 X 103/cubic mm |
Segmented Neutrophils Lymphocytes Monocytes Band neutrophils Eosinophils Basophils | 60% 36% 2% 0% 2% 0% |
Sr Sodium | 139 mEq/L |
Sr Potassium | 4.4 mEq/L |
Sr Creatinine | 0.6 mg/dL |
eGFR using CKD-EPI | 136.8 ml/min/1.73m2 |
Sr Bicarbonate | 24 mEq/L |
Sr Chloride | 101 mEq/L |
Total Bilirubin | 1.0 mg /dL |
AST | 16 U/L |
ALT | 18 U/L |
Sr Albumin | 4.0 g/dL |
HBA1C | 7.9% |
Sr Calcium | 10 mg/dL |
Urine dipstick | pH- 5.4 Albumin-nil no blood no WBCs |
24-hour urinary protein | 76 milligrams/day |
What is the MOST LIKELY incorrect statement regarding the hyperfiltration stage of Diabetic Kidney Disease in this patient?
| A. Renal hyperfiltration is usually diagnosed when the GFR is more than 120 ml/min,which corresponds to a renal function that exceeds two standard deviation above mean GFR. | |
| B. Renal hyper filtration usually precedes microalbuminuria in type 1 diabetes mellitus. | |
|
|
C. Renal hyper filtration is considered as a risk factor for future progression to chronic kidney disease (CKD) and end stage renal disease (ESRD) in type 1 DM. |
|
|
D. eGFR equations like MDRD equation can be used predict hyper filtration. |
|
|
The Correct Answer is Option D: eGFR equations like the MDRD equation can be used to predict hyperfiltration.
Explanation:
Supraphysiological elevation in GFR is observed early in the natural history of type 1 and type 2 diabetes mellitus due to glomerular hyperfiltration. Pathogenesis of hyperfiltration in diabetes is complex, with a prominent role for hyperglycemia and distorted insulin levels, especially in early diabetes and pre-diabetes. Dilatation of the afferent (pre-capillary) glomerular arteriole plays an important role in the hyperfiltration response, by raising both the intra-glomerular pressure and renal blood flow.
Direct measurement of GFR is usually required to detect hyperfiltration because estimation equations, such as the Modification of Diet in Renal Disease (MDRD), usually underestimate the true GFR when it is normal or above normal.
Option A: A definite GFR cutoff is lacking. However, renal hyperfiltration is typically defined as a GFR between 120 mL/min and 150 mL/min/1.73 m2, or greater than 2 standard deviations above the mean GFR in normal, healthy individuals.
Option B: Hyperfiltration in diabetes precedes the onset of albuminuria and/or decline in renal function, and predisposes to progressive nephron damage by increasing glomerular hydraulic pressure
Option C: Hyperfiltration alone does not seem to fully explain adverse renal outcomes, as the risk for ESRD in transplant donors is very low. However, in type 1 diabetes, rapid GFR decline is associated with renal hyperfiltration and impaired GFR and may predict progressive DKD before loss of renal function.
Copyright © ABIM Exam World
Created On: 10/30/2018
Last Modified: 10/16/2026
A 19-year-old African American woman comes to the clinic for a follow-up visit. She has been found to have type 1 diabetes mellitus since the age of 12. She has been using an insulin pump for the last 5 years. She reports no hypoglycemic symptoms and monitors blood sugar with a flash glucose monitor. She reports infrequent hypoglycemic episodes, all of which are self-managed. She met with an ophthalmologist for eye screening and has no retinopathy. She exercises regularly for 30 mins. Her vitals show BP 127/66 mmHg. Her BMI is 22.2. Systemic examination is unremarkable.
Her laboratory investigations are as follows.
Characteristic | value |
Hemoglobin | 13.2 gm/L |
WBC count | 7.8 X 10³/cubic mm |
Platelet count | 241 X 103/cubic mm |
Segmented Neutrophils Lymphocytes Monocytes Band neutrophils Eosinophils Basophils | 60% 36% 2% 0% 2% 0% |
Sr. Sodium | 136 mEq/L |
Sr. Potassium | 4.2 mEq/L |
Sr. Creatinine | 0.6 mg/dL |
eGFR using CKD-EPI | 153.1 ml/min/1.73m2 |
Sr. Bicarbonate | 24 mEq/L |
Sr. Chloride | 101 mEq/L |
Total Bilirubin | 1.0 mg /dL |
AST | 16 U/L |
ALT | 18 U/L |
Sr. Albumin | 4.0 g/dL |
HBA1C | 8.2% |
Sr. Calcium | 10 mg/dL |
Urine dipstick | pH- 5.4 Albumin-nil no blood no WBCs |
24-hour urinary protein | 86 milligrams/day |
What is the MOST LIKELY False statement regarding the hyperfiltration stage of Diabetic Kidney Disease in this patient?
| A. Renal hyper filtration is attenuated by SGLT2 inhibition. | |
| B. Renal hyper filtration occurs in both type 1 and type 2 diabetes mellitus. | |
| C. Obesity can also lead to single-nephron hyper filtration. | |
|
|
D. Incretins like GLP-1 and GIP are neutral in terms of altering renal hemodynamics unlike SGLT2 blockers. |
|
|
The Correct Answer is Option D. Incretins like GLP-1 and GIP do not alter renal function like SGLT2 blockers.
Supraphysiologic elevation in GFR is observed early in the natural history of type 1 and type 2 diabetes mellitus due to glomerular hyperfiltration. The pathogenesis of hyperfiltration in diabetes is complex, with a prominent role for hyperglycemia and altered insulin levels, especially in early diabetes and pre-diabetes. Dilation of the afferent (pre-capillary) glomerular arteriole plays an important role in the hyperfiltration response by raising both intra-glomerular pressure and renal blood flow.
The effects of incretins can be demonstrated experimentally using GLP-1 receptor agonists (GLP-1RA) and dipeptidyl peptidase (DPP)–4 inhibitors, which are associated with renal hemodynamic effects beyond glycemic control. These observations are attributed to GLP-1–mediated inhibition of NHE3 (which assembles with DPP-4 in the proximal tubular brush border), reducing proximal sodium reabsorption and GFR by activating TGF (tubuloglomerular feedback).
Option A: In an 8-week study, empagliflozin in T1DM patients with whole-kidney hyperfiltration (mean GFR 172±23 ml/min per 1.73 m2) demonstrated a glucose-independent 19%decrease in GFR, which was associated with a decline in ERPF (estimated renal plasma flow) and estimated glomerular pressure and an increase in afferent arteriolar resistance, as assessed by the Gomez equations. SGLT2 inhibition could reduce (single-nephron) hyperfiltration in diabetes by restoring sodium-chloride concentration at the macula densa and subsequent TGF-mediated afferent arteriolar vasoconstriction.
Option B: Reported prevalence of hyperfiltration at the whole-kidney level varies greatly: between 10% and 67% in type 1 diabetes mellitus (T1DM) (with GFR values up to 162 ml/min per 1.73 m2), and 6%–73% in patients with type 2 diabetes (T2DM) (up to 166 ml/min per 1.73 m2).
Option C: Independent of diabetes and glucose levels, body weight also augments GFR (by about 15% in obese to about 56% in severely obese non-diabetic subjects).
Copyright © ABIM Exam World
Created On: 10/31/2018
Last Modified: 10/16/2026
A 68-year-old Caucasian gentleman comes to the clinic for a follow-up visit. He is known to
have type 2 diabetes mellitus for the past 18 years. His father had diabetes from age 40 and developed kidney disease requiring dialysis after 15 years
of diabetes. He reports no symptoms. He has had hypertension and
coronary artery disease with a history of PCI 2 years ago. He has
non-proliferative diabetic retinopathy. His medications are sitagliptin,
gliclazide and metformin, in addition to losartan and hydrochlorothiazide. He monitors blood sugar at home and reports no hypoglycemia. He
exercises at least 30 minutes per day. His vitals recording shows BP
of 168/66 mm Hg. His BMI is 29.2. Systemic examination is unremarkable.
His laboratory investigations are as follows.
Characteristic | value |
Hemoglobin | 12.2 gm/L |
WBC count | 6.8 X 10³/cubic mm |
Platelet count | 241 X 103/cubic mm |
Segmented Neutrophils Lymphocytes Monocytes Band neutrophils Eosinophils Basophils | 60% 36% 2% 0% 2% 0% |
Sr. Sodium | 139 mEq/L |
Sr. Potassium | 4.9 mEq/L |
Sr. Creatinine | 1.2 mg/dL |
Sr. Bicarbonate | 22 mEq/L |
Sr. Chloride | 101 mEq/L |
Total Bilirubin | 1.0 mg /dL |
AST | 16 U/L |
ALT | 18 U/L |
Sr. Albumin | 4.0 g/dL |
HBA1C | 7.8% |
Sr. Calcium | 10 mg/dL |
Urine dipstick | pH- 5.4 Albumin-trace no blood no WBCs |
24-hour urinary albumin | 200 milligrams/day |
What is the MOST LIKELY correct statement regarding the clinical diagnosis of Diabetic Kidney Disease in this patient?
|
|
A. Diabetic Kidney Disease previously called as diabetic nephropathy can be diagnosed clinically with renal biopsy only. |
| B. Presence of microalbuminuria is adequate for clinical diagnosis of Diabetic Kidney Disease. | |
| C. Presence of hematuria without non-diabetic kidney disease is impossible in Diabetic Kidney Disease as diabetic kidney disease is a non-proliferative glomerular disease. | |
|
|
D. Family history of Diabetic Kidney Disease is associated with renal involvement in Diabetes. |
|
|
The Correct Answer is
Option D: Family history of Diabetic Kidney Disease is associated with renal
involvement in Diabetes.
Familial studies have demonstrated clustering of diabetic nephropathy. Patients with DM who have a first-degree relative with T1/T2DM and diabetic nephropathy have a higher risk of developing diabetic nephropathy than those without an affected relative. This familial clustering has also been well documented in the Pima Indian population. Candidate genes include glucose transporter 2 (GLUT2), transforming growth factor beta (TGF-?, and endothelial nitric oxide synthase (eNOS).
Option A: Diabetic nephropathy is a clinical syndrome characterized by the following:
·
Persistent
albuminuria (>300 mg/d) that is confirmed on at least 2 occasions 3-6 months
apart
·
Progressive
decline in the glomerular filtration rate (GFR)
·
Elevated
arterial blood pressure
Option C: Microhematuria has been demonstrated in biopsy studies with isolated diabetic nephropathy. Red blood cell casts have also been described in patients with diabetic nephropathy. However, it is important to rule out other glomerular and extra-glomerular causes of hematuria.
Copyright © ABIM Exam World
Created On: 10/31/2018
Last Modified: 10/16/2026
A 30-year-old man was on hemodialysis for 6 months. He was an IV drug user and was diagnosed with HIV. His elder sister came forward as a potential kidney donor for him. He underwent a successful kidney transplant. Which of the following statements is true regarding kidney transplantation in HIV positive individuals and acute rejection episodes?
|
|
A. The episodes of acute rejection are more in HIV positive individuals compared to non-HIV positive patients. |
| B. The episodes of acute rejection are same in HIV positive individuals when compared to age and disease matched non-HIV counterparts. | |
| C. Cyclosporine is a preferred CNI as it has some invitro antiviral properties. | |
| D. There is a documented interaction between CNI and integrase inhibitors. Integrase inhibitors increase the CNI level. | |
| E. There is a proven benefit of using rATG for induction immunosuppression over anti IL-2 therapy to prevent rejections. |
|
|
Correct Answer. Option A. The episodes of acute rejection are more common in HIV positive individuals compared to non-HIV-positive patients.
Explanation.
Kidney transplant recipients with HIV have a high frequency of rejection. In a large, multicenter trial, one- and three-year rejection rates were 31% and 41%, respectively, compared with an expected one-year rejection rate of 12%, as reported by SRTR for all kidney transplant recipients. At European transplant centers, where most patients are induced with interleukin (IL)-2 receptor antibodies, one-year acute rejection rates among recipients with HIV have ranged from 15 to 44 %.
The higher rate of rejection in recipients with HIV is likely multifactorial. Drug-drug interactions between calcineurin inhibitors (CNIs) and protease inhibitors (PIs) can reduce immunosuppressive drug exposure to subtherapeutic levels. Patients on a CNI and PI require nonstandard dosing schedules (i.e., every other or every third day), which can make adherence difficult. Furthermore, concomitant administration of a PI and CNI results in a 40% lower area under the curve (AUC) for CNI exposure at the same CNI target level, leading clinicians to underdose patients taking both medications systematically. Many transplant physicians transition patients off PI-based regimens whenever possible to integrase inhibitor-based regimens, which avoid these drug-drug interactions and allow standard immunosuppression dosing.
HIV-infected transplant recipients, compared with HIV-negative recipients, have a higher risk of acute rejection and, therefore, would theoretically benefit from antibody induction therapy. However, given the underlying immunosuppressed state of HIV-infected patients, prolonged lymphocyte depletion with antibody induction therapy could potentially increase their risk of developing opportunistic infections. Some centers avoid the use of antibody induction therapy among HIV-infected transplant recipients. In centers that use antibody induction therapy, some use basiliximab (an IL-2 receptor antibody) based on data from two studies of HIV-infected kidney transplant recipients that demonstrated an increased risk of infection among those treated with rATG-Thymoglobulin. Other centers prefer to use rATG-Thymoglobulin given its superior efficacy in preventing acute rejection in HIV-negative recipients.
Copyright © ABIM Exam World
Created On: 05/12/2020
Last Modified: 10/12/2026
A 45-year-old female is waitlisted for a kidney transplant. Her native kidney disease is IgA nephropathy. Her blood group is B, and her CPRA is 90%. You are seeing her in the clinic as part of kidney transplant work. As part of documentation, you discuss with her the Public Health Service – Increased Risk Donors (PHS-IRD). You explain PHS-IRD and ask whether she consents. Your rationale is the long wait time for blood group B in your allocation area, especially under CPRA 90%. Which of the following statements regarding the PHS-IRD is TRUE?
| A. As per the new guidelines there is no need to take an informed consent for PHS-IRD from the potential recipient. | |
|
|
B. PHS-IRD kidneys have a discard rate of 2.5-fold. |
| C. The kidney from PHS-IRD have an infection transmission risk anywhere between 10-15% depending on the type of infection. | |
| D. Recipient who received IRD kidneys have increased risk of death at 6 months compared to those who declined the offer. | |
|
|
E. There is increased risk of allograft loss in recipients of PHS-IRD kidneys. |
|
|
Correct Answer. Option B. PHS-IRD kidneys have a discard rate of 2.5-fold.
Explanation.
The United States Public Health Service (PHS) redefined donors who were previously classified by the Centers for Disease Control and Prevention as being at increased risk for transmission of hepatitis B virus (HBV), hepatitis C virus (HCV), and HIV. The number of deceased donors that are part of this classification has increased dramatically because of the opioid epidemic, comprising over 20% of donor kidneys. Overall, overdose-death donors accounted for 1.1% of organ donors in 2000 and 13.4% in 2017. Importantly, transplantation candidates and providers should be well versed in the very low risk of disease transmission from these donors, all significantly < 1% even under the highest-risk circumstances (intravenous drug overdose, syringe-on-person). Unfortunately, “PHS increased-risk donor” (IRD) status is independently associated with nearly 2.5-fold increased odds of turndown. An analysis by Bowring et al. used SRTR data from 104,998 kidney transplantation candidates who were offered IRD kidneys that were eventually accepted. The median KDPI of these kidneys was 30 (interquartile range, 16–49). Importantly, after 5 years, only 31.0% of candidates who declined IRDs received non-IRD DDKTs later; the median KDPI of these non-IRD kidneys was 52. Those who accepted an IRD had a substantially lower risk of death at 1 to 6 months after decision (aHR, 0.50; 95% CI, 0.67 to 0.90; P=0.006) and beyond 6 months after decision (aHR, 0.46; 95% CI, 0.52 to 0.58; P< 0.001). A single-center report of PHS-IRD kidney utilization reviewed offers made to 2423 kidney transplant candidates from June 2004 to May 2005; 1502 ultimately received a transplant with or without a PHS-IRD kidney. Accepting a PHS-IRD kidney offer was associated with lower mortality (3.63% versus 11.6%; aHR, 0.467; P = 0.0008) and a lower risk of allograft loss than in non–PHS–IRD recipients (P = 0.007), with no transmission of HCV, HBV, or HIV.

Copyright © ABIM Exam World
Created On: 05/12/2020
Last Modified: 10/12/2026
All the following drugs cause hyperkalemia. All the drugs act by a specific mechanism to induce hyperkalemia. Only one drug acts through a different mechanism. Which drug induces hyperkalemia via a different mechanism than the others?
|
|
A. Heparin. |
| B. Low molecular weight heparin. | |
| C. Aminoglutethimide. | |
| D. Dabigatran. | |
|
|
E. Calcineurin inhibitors. |
|
|
Correct Answer. Option D. Calcineurin inhibitors.
Explanation.
Heparin, low-molecular-weight heparin, Aminoglutethimide and Dabigatran all impair adrenal hormone metabolism. These drugs cause potent inhibition of adrenal hormone synthesis, leading to hyperkalemia.
The hyperkalemia seen with calcineurin inhibition is likely multifactorial and relates to inhibitory effects on Na+-K+-ATPase in collecting ducts and possibly to distal tubular acidosis. In addition, there is evidence that decreased numbers of mineralocorticoid receptors, which are detected in 75% of patients who are treated with cyclosporine, lead to hyperkalemia and metabolic acidosis as a result of aldosterone resistance. Recently, it was demonstrated that cyclosporine reduces paracellin-1 expression in thick ascending limb cells. This decrease in magnesium transport likely contributes to the magnesium wasting and hypomagnesemia induced by cyclosporine, which is associated with chronic interstitial fibrosis, faster decline in kidney function, and increased rates of graft loss in renal transplant recipients with CNI nephrotoxicity. Finally, it was shown that cyclosporine indirectly opens ATP-sensitive K+ channels by inhibiting calcineurin, which could contribute to the CNI-associated hyperkalemia.
Copyright © ABIM Exam World
Created On: 05/18/2020
Last Modified: 10/12/2026
A 25-year-old man is referred to you for evaluation of nephrotic syndrome. A kidney biopsy is done, and it shows minimal change disease. His BP is 150/90 mmHg, and his heart rate is 70 bpm. His current medications are prednisone 40 mg once daily, furosemide 40 mg twice daily, Ramipril 10 mg once daily, and Calcium + vitamin D supplementation. Clinical exam shows raised JVD 3 + pitting edema to the right thigh. His blood work shows serum creatinine 0.9 mg/dL, BUN 35 mg/dL, and serum potassium 3.2 mEq/L. Urine analysis is bland, and his 24 hr urine protein is 5.8g. He is strictly following his salt restriction. At the 1-month follow-up, his proteinuria has decreased to 4.0 g/24 hrs, but his foot edema remains unchanged. Serum albumin improved from 1.9 g/L to 2.8 g/L. Which of the following drugs will benefit the patient?
| A. Metolazone. | |
| B. Amiloride. | |
| C. Chlorthalidone. | |
| D. Cyclophosphamide. | |
| E. Amlodipine. | |
| F. Losartan. |
|
|
Correct Answer. Option B. Amiloride.
Explanation.
Two major factors, both of which lead to retention, have been thought to be responsible for the development of edema in patients with nephrotic syndrome; both likely contribute to a variable degree in individual patients:
Distinguishing between these mechanisms is clinically important because it affects tolerance of diuretic therapy. Diuretics are well tolerated in patients with renal sodium retention but, if underfilling is the primary mechanism, can lead to worsening hypovolemia as evidenced clinically by an elevation in serum creatinine.
Studies in experimental animals with unilateral nephrotic syndrome or glomerulonephritis suggest that primary sodium retention in these disorders is due to increased sodium reabsorption in the collecting tubules, which is also the site of action of atrial natriuretic peptide (ANP) and the related renal hormone urodilatin. This is called the overfill hypothesis because primary renal sodium retention leads to volume expansion.
Increased activity of the epithelial sodium channel (ENaC) may contribute to sodium retention. Serine proteases are aberrantly filtered in nephrotic syndrome, increasing their concentration in the urine. Plasminogen (which is activated by epithelial urokinase-type plasminogen activator [uPA] to plasmin) in nephrotic urine may activate ENaC via proteolytic cleavage of the gamma chain, providing a potential mechanism by which filtered proteins cause sodium retention. It also explains the observation that remission from the nephrotic syndrome is generally preceded by a decrease in urinary protein excretion. In an animal model of nephrotic syndrome, mice treated with the serine protease inhibitor aprotinin normalized urinary serine protease activity and prevented sodium retention. A similar result was seen when rats with nephrosis were treated with the ENaC inhibitor amiloride.
Hence, amiloride is the best answer for this clinical vignette.
Copyright © ABIM Exam World
Created On: 05/18/2020
Last Modified: 10/12/2026
A 68-year-old Hispanic woman is referred to you for evaluation of nephrotic syndrome. She has a history of type 2 diabetes and hypertension. Both diabetes and hypertension are well controlled. Her serum creatinine is 2.1 mg/dL. Urinalysis shows only proteinuria, with a protein-to-creatinine ratio of 6. A renal biopsy shows amyloidosis and interstitial fibrosis. Based on the history, biopsy findings, and proteinuria above, which diagnostic test would you order to characterize the type of her amyloidosis?
| A. Electron microscopy of the glomerulus. | |
| B. Immunofluorescent studies. | |
| C. Immunofixation study. | |
|
|
D. Amyloidosis derived from leukocyte chemotactic factor 2 (ALECT 2). |
| E. No further testing. |
|
|
Correct Answer. Option D. Amyloidosis derived from leukocyte chemotactic factor 2 (ALECT2).
Explanation.
ALECT2 amyloidosis is a systemic form of amyloidosis with predominantly renal and liver involvement. Most reported cases in North America (88 to 92 %) occur in older Hispanic adults of Mexican origin. However, Punjabis, First Nations people in British Columbia, and Native Americans also have a predisposition for this disorder. In one study of renal amyloidosis among Egyptians, ALECT2 amyloidosis was the second most common form of renal amyloidosis behind AA and ahead of AL amyloidosis. Cases have also been reported in Pakistani, Sudanese, and Chinese patients. The pathogenesis of ALECT2 amyloidosis remains poorly understood. Patients typically present with chronic kidney disease (CKD) and variable proteinuria; nephrotic syndrome is uncommon. Diagnosis requires a kidney biopsy, preferably with laser microdissection and mass spectrometry. Patients with ALECT2 amyloidosis characteristically have diffuse Congo red-positive amyloid deposition in the cortical interstitium, with variable glomerular and vascular involvement. Overall, patients with ALECT2 amyloidosis have better survival than those with AL or AA amyloidosis, possibly because cardiac involvement is absent or rare. However, renal survival is relatively poor, with up to 39 percent of patients progressing to end-stage renal disease (ESRD). There are no specific therapies for ALECT2 amyloidosis.
Copyright © ABIM Exam World
Created On: 05/19/2020
Last Modified: 10/12/2026
A 50-year-old male is referred for evaluation of high-grade proteinuria. He does not have diabetes but is known to have hypertension. He takes hydrochlorothiazide 12.5 mg once daily for that. The blood and urine tests are shown below. You perform a kidney biopsy, and it shows focal segmental glomerulosclerosis (FSGS). The concern is whether this is primary vs. secondary FSGS. Which of the following options would be supportive of secondary FSGS as opposed to primary FSGS?
Value | Test |
11.2 gm/L. | Hemoglobin |
6,800 cells/cumm | WBC count |
2,41,000 cells/cumm | Platelet count |
139 mEq/L. | Sr. Sodium |
5.2 mEq/L. | Sr. Potassium |
1.6 mg/dL. | Sr. creatinine |
22 mEq/L. | Sr. Bicarbonate |
101 mEq/L. | Sr. Chloride |
4.0 g/dL. | Sr. Albumin |
10 mg/dL. | Sr. Calcium |
p: 5.4. Albumin-++++ No blood. No WBCs. | Urine |
3.8 grams/day.
| 24-hour urinary protein |
Negative
| ANCA |
Negative
| ANA |
No monoclonal proteins | Serum protein electrophoresis |
negative | HIV |
negative | HbsAg |
negative | Anti HCV |
| A. Increase in mesangial matrix. | |
| B. Focal sclerosis only in some parts of the glomerulus in primary FSGS. | |
|
|
C. Serum albumin and width of foot processes (effacement of foot processes). |
| D. Tram-tract appearance of the basement membrane. |
|
|
Correct Answer. Option C. Serum albumin and width of foot processes (effacement of foot processes).
Explanation.
The causes of FSGS may be primary (idiopathic) or secondary. Secondary forms are generally characterized by glomerular hyperfiltration and hypertrophy. It was suggested that serum albumin and the degree of foot processes effacement can distinguish primary from secondary forms of FSGS. Praga et al. reported that serum albumin levels are <3 g/dL in those with biopsy-proven primary FSGS, compared to
>3.5 g/dL in those patients with secondary FSGS. A histopathologic study by Deegens et al. showed that foot process width is significantly higher (3200 nm) in primary FSGS than in secondary FSGS (1098 nm; normal 562 nm). Overall, foot process width over 1500 nm differentiated idiopathic from secondary FSGS with high sensitivity and specificity. This suggests that patients with primary FSGS have complete effacement of foot processes, whereas secondary FSGS shows patchy effacement.
In a study of 46 patients with an FSGS lesion, patients were divided by the degree of foot process effacement observed on kidney biopsy. Patients were categorized as having diffuse (?80 %) or limited (<80 %) foot process effacement. Compared with patients with limited foot process effacement, those with diffuse foot process effacement without an identifiable cause had lower serum albumin levels and higher proteinuria and were more likely to have nephrotic syndrome on presentation (100 vs 4 %). Based upon these results, patients who presented with diffuse foot process effacement without an identifiable cause and nephrotic syndrome were classified as primary FSGS. Patients with segmental foot process effacement, with or without an identifiable cause, or diffuse foot process effacement due to an identifiable cause were classified as secondary FSGS.
Copyright © ABIM Exam World
Created On: 05/19/2020
Last Modified: 10/12/2026
All of the following help predict AV Graft stenosis EXCEPT:
| A. Hyperpulsatility of the AV Graft | |
| B. Reduced pulse augmentation | |
| C. Increased bleeding and clots | |
| D. Decreased KT/V | |
| E. Decreased Blood Flow rate | |
|
|
F. Surveillance of the graft |
|
|
Copyright © ABIM Exam World
Created On: 09/23/2020
Last Modified: 10/12/2026
A 20-year-old male was at a party where, after dancing, he ate a lot of cake because it was “delicious”. After 2-3 hours, he developed a sudden onset of weakness in all 4 limbs. He has had two similar episodes before. He was rushed to the nearest ER. On examination: P: 88/min, BP: 140/96 mm Hg, Pallor+, no thyroid enlargement. He is alert and oriented. No cranial nerve involvement or neck muscle weakness. Motor power is grade 2-3 in all extremities, reflexes sluggish to absent. Sensory exam is normal. Laboratory results reveal the following:
pH 7.4
pCO2 40 mm Hg
PaO2 98 mm Hg
HCO3 24 mEq/L
O2 saturation 98%
Na 140 mEq/L
K 2.2 mEq/L
Cl 103 mEq/
BUN 10 mg/dl
S.Cr 0.8 mg%
S. Ca 10.2 mg/dl
PO4 2.5 mg/dl
Mg 2.2 mg/dl
Urine Electrolytes
Urine Na 100 mEq/L
Urine K 15 mEq/L
Which of the following is the MOST likely diagnosis?
|
|
A. Familial periodic paralysis. |
| B. Renal tubular acidosis | |
| C. Primary hyperaldosternism. | |
| D. Thyrotoxic periodic paralysis |
|
|
Copyright © ABIM Exam World
Created On: 09/12/2017
Last Modified: 10/17/2026
A 35-year-old Caucasian male presents with persistent swelling of both legs associated with dark colored urine for two months. He went to an emergency room 2 months ago for these complaints and was told that he had some protein and blood in the urine. He was treated with levofloxacin for 3 days. There is no other past medical history. No history of skin rash or joint swelling. On examination, blood pressure was 130/85 mm Hg, and there was bilateral 1+ pedal edema. Urine analysis showed 3+ proteinuria, 10-15 RBCs per high-power field, and occasional RBC casts. The BUN was 10 mg/dL, and serum creatinine was 0.9 mg/dL. Antistreptolysin was negative; C3 was decreased, and C4 was normal. Antinuclear antibodies, ANCA and hepatitis B and C serology were negative. 24-hour urine collection showed 2 g proteinuria, and a kidney biopsy was performed. Light microscopy showed increased light-staining matrix, and the glomerular basement membrane appeared irregularly thickened. Silver stain revealed a regular basement membrane in multiple glomeruli. Immunofluorescence showed positive staining for C3, but negative for IgG, IgM and IgA. Electron microscopy revealed electron-dense deposits in the mesangium and subendothelial area.
What is the most likely diagnosis?
| A. Acute poststreptococcal glomerular nephritis | |
| B. Diffuse proliferative lupus nephritis | |
| C. Dense deposit disease | |
|
|
D. C3 glomerulopathy |
| E. |
|
|
Copyright © ABIM Exam World
Created On: 09/12/2017
Last Modified: 10/17/2026
A 25-year-old male comes to the physician complaining of flank pain and hematuria. He says the pain is constant and dull. There is no frequency, urgency or dysuria. has a history of mental retardation and seizures. O physical exam, his blood pressure is 140/90 mm Hg, and his pulse is 80 bpm. He has multiple yellow papules on his nose and cheeks and numerous aranched skin spots on his face. A 2-3 cm hypopigmented macule is noted on the right arm. CT scan of the head was done as the patient presented with seizures. CT head w s reported normal. CT scan o the abdomen shows bilateral hypodense, fat-containing genital masses and cysts.
What is the MOST likely diagnosis associated with these findings?
| A. Von Hippel Lindau | |
| B. Sturge Weber Syndrome | |
|
|
C. Tuberous Sclerosis |
| D. Osler Weber Rendu | |
| E. Neurofibromatosis type 2 |
|
|
Copyright © ABIM Exam World
Created On: 09/13/2017
Last Modified: 10/17/2026
A 15-year-old boy is brought to the ER by his foster mother, who states that when she got home from work, she noticed he was acting very strange. He had slurred speech and seemed confused. He appeared very uncoordinated, and she was unsure whether he had fallen or hit his head. She states that he is somewhat a troubled boy but doesn’t know much about his history, as he has been in and out of the foster care system out of state. On physical exam, he is tachycardic and has tachypnoea. Pupils are dilated, but there is no nystagmus. Fundoscopic exam shows optic disc hyperemia. He is relatively uncooperative but not aggressive or hostile. When asked about suicidal thoughts, he responds only with inaudible mumbling. His foster mother left for work 10 hours prior and assumed he left for school. She is unsure when these symptoms began or what may have triggered them. P is 105/ min, BP is 140/90 mm Hg, RR is 28/min, and T is 97.1 F. Laboratory examination is as follows:
Na 135 mEq/L
K 5.0 mEq/L
CL 105 mEq/L
BUN 19 mg/dL
Cr 1.3 mg/dL
HCO3 8 mEq/L
Glucose 100 mg/dL
pH 7.3
pO2 90 mmHg
pCO2 22 mmHg
Measured serum osmolarity: 320 mmol/L
What is the next step in management?
| A. Gastric lavage | |
| B. N-acetylcystiene and activated charcoal | |
| C. Fomepizole | |
|
|
D. Fomepizole and Hemodialysis |
|
|
E. Obtain serum levels of salycylate, methanol and ethylene glycol levels |
|
|
Copyright © ABIM Exam World
Created On: 09/13/2017
Last Modified: 10/17/2026
All of the following help predict AV Graft stenosis EXCEPT:
|
|
A. Hyperpulsatility of the AV Graft |
| B. Ruduced pulse augmentation | |
| C. Increased bleeding and clots | |
| D. Decreased KT/V | |
| E. Decreased Blood Flow rate | |
|
|
F. Surveillance of the graft |
|
|
Copyright © ABIM Exam World
Created On: 09/14/2017
Last Modified: 10/17/2026
A 40-year-old pleasant African man with ESRD secondary to FSGS started automated peritoneal dialysis. His prescription includes 2.5 L and 3 exchanges over 8 hours at night, with a last fill of 2 L. His urine output is 1000 mL/day. A typical ultrafiltration on the cycler is used at 1000 mL. The average drain volume during the day dwell was 1500 mL before going on the cycler at night.
He came with complaints of lower abdominal wall edema extending to the scrotum over the past 5 days. Without any change in the dialysis prescription, his drain volume before going on the cycler dropped to 900 mL, and the ultrafiltration volume on the cycler came down to 100 mL. He reports no pain with fill or drain.
What is the next step?
| A. Chest X ray PA and lateral view | |
| B. Drain the fluid middle of the day to reduce the dwell time | |
| C. PD catheter manipulation | |
|
|
D. Abdominal CT scan with contrast in the dialysate |
| E. Switch to hemodialysis | |
| F. Pleurodesis |
|
|
Copyright © ABIM Exam World
Created On: 09/14/2017
Last Modified: 10/17/2026
Cyclosporine nephrotoxicity in a renal transplant recipient is associated with all the following renal biopsy findings EXCEPT:
(THIS PICTURE BELOW IN LOW POWER SHOWS ONE OF THE CLASSICAL FINDINGS IN CSA TOXICITY)

| A. Interstitial Fibrosis | |
| B. Tubular atrophy | |
| C. Endothelial cell swelling | |
|
|
D. Glomerular thrombin deposits |
| E. Glomerular basement membrane thickening | |
|
|
F. Double contours of the GB |
|
|

Copyright © ABIM Exam World
Created On: 09/14/2017
Last Modified: 10/17/2026
A 68-year-old African American male with a known history of diabetes mellitus, hyperlipidemia, CVD, and GERD presents to the ER with chest pain and shortness of breath. The patient says the pain is crushing and radiates to his left arm. It woke him from sleep 30 minutes ago. He took his antacids and 4 tablets of nitroglycerin, and the pain got better. His current medications include low-dose aspirin, metoprolol, glyburide, pioglitazone, lisinopril, simvastatin, and omeprazole. He recently suffered an upper respiratory infection for which he was given Levofloxacin. Vitals: BP 160/95 mm Hg, T 98.1, HR 110. He has no leg edema and no jugular venous distention. EKG shows LVH by voltage criteria with an isoelectric ST segment. Serial troponin levels are normal. A stress test showed evidence of stress-induced ischemia in the anterior leads. He is scheduled for cardiac catheterization the next day. Laboratory results are as follows:
Serum Chemistry:
Na 143 mEq/L
K 3.5 mEq/L
Cl 101 mEq/L
HCO3 22 mEq/L
BUN 35 mg/dL
Cr 3.0 mg/dL
Glucose 110 mg/dL
What would you do to PROTECT the kidneys before doing the cardiac catheterization?
| A. Dopamine IV infusion before and after the procedure. | |
| B. Nifedipine. | |
|
|
C. Isotonic sodium bicarbonate infusion before and after the procedure. |
| D. N Acetyl Cysteine before and after the procedure | |
| E. Start mannitol IV before the procedure | |
| F. Left ventriculogram quickly with coronary angiogram |
|
|
Copyright © ABIM Exam World
Created On: 09/14/2017
Last Modified: 10/17/2026
As per the JNC VIII committee recommendation, for individuals who are part of the African American population, including those with diabetes, the initial treatment should include a thiazide-type diuretic or calcium channel blocker (CCB).
Which of the following thiazide-type diuretics is preferred as the initial antihypertensive therapy?
| A. Hydrochlorthiazide | |
|
|
B. Chlorthalidone |
| C. Indapamide | |
| D. Metalazone | |
| E. Polythiazide |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
Which of the following antihypertensive medications resulted in better blood pressure control and cardiovascular outcomes when combined with an ACE inhibitor?
| A. Beta blocker | |
|
|
B. Calcium channel blocker |
| C. Angiotensin Receptor Blocker | |
| D. Diuretics |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
The ACCOMPLISH trial is the first major trial addressing the issue of combination therapy in 11,506 patients who were at high cardiovascular risk. The goal blood pressure was <130/80 mm Hg in patients with diabetes or impaired renal function, and <140/90 mm Hg in patients with prior cardiovascular disease.
Which of the following combinations of blood pressure medications was the best in reducing cardiovascular events and slowing the progression of nephropathy in patients with hypertension who were at high risk for such events?
| A. ACEI + Diuretics | |
|
|
B. ACEI + CCB |
| C. ACEI + Beta-blocker | |
| D. CCB + Beta-blocker |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
An 18-year-old male is brought to the renal clinic for evaluation of hypertension. There is no history of edema of the feet, puffiness of the face, hematuria, oliguria or recurrent urinary tract infections. He is an active football player, but lately he complains of weakness and muscle cramps. His blood pressure for the last 3-4 years has always been borderline high and during this visit was as noted below.
Physical examination shows: Pulse 100/min; all peripheral pulses are well felt. BP 150/100 mm Hg, Temp. 37.4 degrees C. He is pale. His growth is stunted. His cognitive function is normal, and no focal neurological deficits are noted. Other systems are unremarkable. Laboratory examination is as follows:
Hemoglobin 13.5 g/dL
Hematocrit 42%
Platelet Count 150,000 mm3
White Blood Cells 8,000 mm3
Urinalysis:
Protein 100 mg/24 h
Glucose None
Red Blood Cells None
White Blood Cells None
Leukocyte Esterase Negative
Nitrites Negative
Chemistry:
BUN 13.5 mg/dL
Creatinine 0.9 mg/dL
Sodium 140 mEq/L
Potassium 5.8 mEq/L
Bicarbonate 18.5 mEq/L
Chloride 112 mEq/l
Calcium 9.2 mEq/L
Phosphorus 3.2 mg/dL
Aldosterone 5 ng/mL
PRA <1.0 ng/dL/hr
Glucose 100 mg/dL
HbA1C 5.30%
S. Osmolality 282 mOsmol
Uric Acid 5.3 mg/dL
ESR 9.8 mm/h
ABG:
pH 7.25
PCO2 32 mm Hg
HCO3 16 mEq/L
PO2 90 mm Hg
U: Normal-sized kidneys, no hydronephrosis
Considering the history and the laboratory findings, which of the following is most likely the cause of hypertension in this patient?
| A. Liddle's Syndrome | |
|
|
B. Gordon's Syndrome |
| C. Congenital adrenal hyperplasia | |
| D. Glucocorticoid-remediable aldosteronism | |
| E. Mineralocorticoid receptor activating mutation |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
A 56-year-old male was brought to the emergency room with drowsiness and lethargy. He has had these symptoms for the past 2 days. He complains of a recent history of anorexia, nausea, and vomiting. He has diabetes mellitus and has been on glimepiride 1 mg daily for the last 4 years. One week ago, he had decreased vision with redness in his right eye. He was treated by his ophthalmologist with drops,s which seem to have resolved the problem. He currently takes cholecalciferol weekly for osteoporosis. On physical examination,n his pulse is 80/min, blood pressure is 140/90 mm Hg, respiratory rate is 20/min, and temperature is 97.7°F. The patient appears drowsy but shows no focal neurological deficits. Review of systems is otherwise unremarkable. Urinalysis is positive for glucose and negative for proteinuria, WBCs and RBC casts.A24-hour urinary protein collection shows proteinuria of 3.5 g/day. Further labs reveal:
Hemoglobin 8 gm%
Hct 24%
MCV 85
WBC 7800/ml
PMN 80%
Lymphocytes 20%
ESR 80 mm/hr
Na 145 mEq/L
BUN 80 mg/dL
Cr 1.8 mg/dL
CL 115 mEq/L
HCO3 25 mEq/L
Uric acid 5.8 mg/dL
Ca 14 mg/dl
PO4 2.8 mg/dL
Total Protein 7.8 gm/dL
Albumin 3.5 mg/dL.
Vitamin D 40 ng/ml
PTH 10 pg/ml
Which of the following is most likely the cause of his hypercalcemia?
| A. Vitamin D toxicity | |
| B. Primary hyperparathyroidism | |
|
|
C. Multiple myeloma. |
| D. Sarcoidosis |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
A 25 year-old female is referred by her primary care provider for evaluation of hypertension and hypokalemia. The primary care provider has already started her on oral potassium, despite therapy her Potassium being 2.8 meq/L. Her blood pressure despite treatment with amlodipine and Lisinopril 154/96 mm of Hg. There is no renal bruit. Systemic and fundus examinations are normal. Her mother was also diagnosed with hypertension at an early age. Her brother died of a cerebrovascular accident 2 years ago. Laboratory findings are as follows:
Na 140
Potassium 2.8
Chloride 100
HCO3 26
BUN 15
Creatinine 0.8
Glucose 110
TSH and Cortisol are normal
ACTH elevated
Renin 0.7 (Low)
Aldosterone 48 (elevated)
Urinalysis:
Sodium 240 mEq/D
Potassium 98 mEq/D
Urinary 18-OH Cortisol and 18-oxocortisol are elevated.
The most appropriate treatment for this patient is:
| A. Steroids | |
| B. Spironolactone | |
|
|
C. Steroids + Spironolactone |
| D. Amiloride |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 08/06/2018
A 60-year-old with recently diagnosed colon cancer and diabetes presents with bilateral pedal edema; BP is 120/80 mm Hg. Urinalysis showed 4+ protein, no RBCs or WBCs, and 8-10 Hyaline casts. His BUN is 20, Creatinine is 1 mg/dL, and albumin is 2 grams/dL. A 24-hour urine collection showed 10 grams of protein. The patient undergoes a kidney biopsy. The EM is shown below :

What is the most likely diagnosis?
| A. Crescentic GN | |
| B. IgA nephropathy | |
| C. Minimal change disease | |
| D. Focal segmental glomeruloscerosis | |
|
|
E. Membranous nephropathy |
| F. Diabetic nephropathy |
|
|
The correct answer is E
Membranous Nephropathy.
Electron microscopy shows subepithelial electron-dense deposits, as classically seen in membranous nephropathy. If in the question there is a suggestion of colon, breast, or lung cancer, then the glomerulopathy is usually membranous. Then look for other histopathological findings that confirm the diagnosis: subepithelial electron-dense deposits.
Explanation:
BOARD POINT - FAMILIARIZE YOURSELF WITH THESE ASSOCIATIONS :
1. Solid cancers (colon, breast, lung, renal) plus proteinuria = Membranous nephropathy
2. Hodgkin's lymphoma plus proteinuria = Minimal change disease
3. HIV plus proteinuria = Focal segment glomerulosclerosis FSGS
4. Pamidronate plus protenuria = FSGS (rare)
5. Myeloma, no albuminuria on dipstick, but proteinuria on protein/creatinine ratio or 24-hour urine: Light chain nephropathy
6. Myeloma with nonspecific proteinuria (dipstick, urine protein/creatinine ratio and 24-hour urine): Light chain nephropathy or amyloidosis.
BOARD POINT - FAMILIARIZE YOURSELF WITH THESE HISTOPATHOLOGY ASSOCIATIONS FOR VARIOUS GLOMERULAR DISEASES
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
You are the nephrologist on call. The ER calls you for an 18-year-old female who is complaining of vomiting and diarrhea. Her serum sodium is 116 mEq/L and Serum potassium is 5.9 mEq/L. On physical examination, the patient is drowsy;p; pulse is 126/min, BP is 90/60 mm Hg, and RR is 32/min. Her chest is clear. Her heart sounds are normal, with no murmurs. The patient is drowsy but arousable, with no focal neurological deficit. Laboratory findings are as follows:
Hb 16 gm/dl
WBC 12,800/cmm
Polymorph 46%
Lymphocytes 16%
Eosinophils 4%
Monocytes 4%
Platelets 2,40,000/cmm.
CL 70 mEq/L
BUN 10 mg/dl
Creatinine 0.5 mg/dl
Na 116 mEq/L
K 5.8 mEq/L
Urinalysis:
pH 6.4
Protein trace
Glucose absent
Microscopic: occasional WBCs & RBCs
Urinary Na 90 mEq/L
Urinary K 20 mEq/L
ABG
PH 7.32
PCO2 36
HCO3 20 mEq/L
PaO2 92
O2 saturation 98%
S. Cortisol 6.00 mg/dl
TSH 3.5 IU/m (Normal 0-5 IU/m ).
Both plasma Renin and Aldosterone are high.
Which of the following conditions is most likely with these findings?
|
|
A. Type 4 RTA |
|
|
B. Pseudo-hypo-aldosteronism Type 1 |
| C. Gordon's syndrome | |
| D. Diarrhea |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
A 32-year-old male is brought to the renal clinic with a history of hematuria, oedema of the feet, and puffiness of the face. He reports fever and sore throat a week ago. He also complains of breathlessness on exertion and oliguria. Physical examination shows: Pulse 100/min, BP 150/100 mm Hg, and Temp. 37.4 C. He is pale. He has facial puffiness and oedema of the feet. Systemic examination-unremarkable. Laboratory examination is as follows:
Hb 10.5 g/d
Hct 34%
Platelet 250,000 mm3
WBC 8,000 mm3
Differential count: P 80% L 12% E 6% M 2%
ESR 9.8 mm/h
Urinalysis:
Protein 3000 mg/24 h
Glucose None
RBC 50-60/hpf Dysmorphic
WBC occasional
Leukocyte Esterase Negative
Nitrite Negative
BUN 40 mg/dL
Creatinine 3.9 mg/dL
Sodium 140 mEq/L
Potassium 4.2 mEq/L
Bicarbonate 25.5 mEq/L
S. protein 5.5 g/dl
S. Albumin 2.5 g/dl
Calcium 9.2 mEq/L
Phosphorus 3.2 mg/dL
Glucose 100 mg/dL
Uric Acid 5.3 mg/dL
C 3 Low
C4 normal
HBsAg /HIV Neg
ANA Neg
Kidney Biopsy: Shows enlarged Glomeruli, lobular accentuation, mesangial hypercellularity, endo-capillary proliferation and double contour along the capillary wall. IF shows bright C3 in the mesangium and capillary wall with absent immunoglobulin staining.
Electron Microscopy: Suggestive of dense deposits.
What is the BEST treatment option for this patient?
| A. Plasma exchange + Rituximab | |
| B. Rituximab | |
|
|
C. Eculuzimab |
| D. Cyclophosphamide + Steroids |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
A 36-year-old female was diagnosed with membranous nephropathy secondary to SLE. Her 24-hour protein excretion was 7.5 gms/day. Her serum creatinine was 0.9mg/dl. She was started on 500 mg of cyclophosphamide IV every 15 days (Euro-Lupus) and prednisolone 1 mg/kg orally per day. After 3 months of therapy, she presented with decreased urine output, puffiness of the face, and oedema of the feet. On physical examination, her temperature was 37°C, blood pressure was 160/100 mm Hg, pulse was 90/min, and respiratory rate was 20/min. She is anemic, with facial puffiness and oedema of the feet. On systemic examination, air entry was decreased at both lung bases, and heart sounds were distant and feeble. Chest X-Ray reveals bilateral pleural effusions. Echocardiogram reveals mild to moderate pericardial effusion. Laboratory examination is as follows:
Hemoglobin 10.0 g/dL
Hematocrit 34%
Platelet Count 150,000 mm3
WBC 8,000 mm3
Differential count: P 80% L 12% E 6% M 2%
ESR 50.8 mm/h
Urinalysis:
Protein 1450 mg/24 h
Glucose None
RBCs 70-80/HPF dysmorphic
WBCs 5-8/HPF
Leukocyte Esterase Negative
Nitrites Negative
BUN 35 mg/dL
Creatinine 3.9 mg/dL
Sodium 140 mEq/L
Potassium 5.2 mEq/L
Bicarbonate 15.5 mEq/L
Calcium 9.2 mEq/L
Phosphorus 5.6 mg/dL
Glucose 100 mg/dL
Uric Acid 5.3 mg/dL
C3 & C4 decreased
ANA positive
dsDNA positive
Repeat biopsy shows:

Which of the following is the most appropriate therapy for her current condition?
| A. Mycophenolate and steroid | |
|
|
B. Mycophenolate, tacrolimus and steroids |
| C. Rituximab | |
| D. I.V Immunoglobulins | |
| E. Plasma exchange |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
A 30-year-old man comes to your office with a painful rash on his neck. He has a fever and malaise. He has a history of IV. He is currently taking Tenofovir, emtricitabine, and indinavir. The rash is suggestive of Herpes Zoster rash :
Physical examination reveals no oral cavity lesions. His current CD4 count is 250/ m3. His chemistry is normal. He is started on an intravenous medication for his rash. Two days later, his chemistry is as follows:
Na 135 mEq/L
K 4.5 mEq/L
CL 100 mEq/L
HCO3 24 mEq/L
BUN 21 mg/dL
Cr 2.0 mEq/L
Glucose 95 mg/dL
Calcium 9.4 mg/dl
Urinalysis shows needle-shaped crystals in the sediment.
Which of the following is most likely the cause of his renal problem?
| A. Indinavir | |
| B. Tumor lysis syndrome | |
| C. Antifreeze ingestion | |
|
|
D. Acyclovir |
| E. IV TMP/SMX |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
In patients with CKD and ESRD, Vitamin D appears to protect against cardiovascular events by controlling secondary hyperparathyroidism. The OPERA trial evaluated the effect of the Vitamin D analog paricalcitol in CKD stages 3-5 with left ventricular hypertrophy. The study observed the effect on left ventricular mass and function.
Which of the following statements is true about the effect of paricalcitol in CKD and ESRD patients?
| A. Paricalcitol treatment reduced LV mass | |
| B. Paricalcitol treatment preserved LV ejection fraction | |
| C. Paricalcitol treatment improved pulse wave velocity and arterial stiffness | |
| D. Paricalcitol treatment improved blood pressure control | |
|
|
E. Paricalcitol treatment significantly reduced PTH and alkaline phosphatase |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
You are rounding on your patients in the dialysis unit and see a 65-year-old gentleman with ESRD due to chronic interstitial disease. He also has a history of diet-controlled diabetes mellitus and hypertension. His other past medical history is significant for dyslipidemia, coronary artery disease, hypothyroidism, gout and depression. He has been hospitalized in the recent past for swelling and pain of his right great toe. He was seen by the foot doctor, a scan was done, and eventually the great toe had to be amputated. He has been on hemodialysis 3 times a week. His weekly Kt/V is 1.9. You are conducting the monthly blood work review for this patient. You note that his hemoglobin has been persistently low over the past few monthly blood draws. He is currently on 100 mcg of Darbepoetin weekly on dial sis. On enquiry, there is no history of blood loss in the form of hematemesis, melena, hematochezia or hemoptysis. Activee medication list includes Losartan, Atorvastatin, Calcitriol, multivitamin supplements, paroxetine, allopurinol, aspirin.
His pertinent blood work is as follows:
Test | Result |
WBC | 4500 cells /cumm |
Hemoglobin | 8.2 g/dL |
Platelet count | 450 thousand /cumm |
Reticulocyte count | Normal |
Iron | 55 (range 50-150) |
Total iron-binding capacity | 250 g/dl (range 250-310) |
Transferrin saturation | 20% |
Ferritin | 1400 ng/ml (range 20-235) |
Haptoglobin | 400 mg/dl (range 83-267) |
Lactate dehydrogenase | 240 U/L (range 80-225) |
Total bilirubin | 1.0 mg/dl |
Folate | 7 ng/ml (range 1.8-9.0) |
B12 | 500 pg/ml (range 200-800) |
Peripheral blood smear. | Normal RBC morphology, few burr cells. |
Which of the following is true about this patient’s anemia?
Omitted
|
Correct Answer: Option C: This patient has a chronic inflammatory state that contributes to his anemia.
Explanation:
10-15% of patients receiving erythrocyte-stimulating agents ESAsAs) develop resistance. Here are multiple reasons why ESRD patients develop resistance.
ESA resistance occurs due to the following reasons:
Iron deficiency.
Chronic inflammation.
Under-dialysis.
Hemolysis.
Folate and B12 deficiency.
Chronic blood loss.
Anti-EPO antibodies.
Pure red cell aplasia.
Failed chronic renal allograft.
ACEI/ARB.
Aluminum overload.
Hyperparathyroidism.
Hematological disorders or malignancy.
Option A: Incorrect option. SRD is associated with erythropoietin deficiency. The patient has already been initiated on ESA. There is no point in measuring EPO levels. There is no evidence that measuring EPO levels is part of anemia management in CKD.
Option B: Incorrect option. SRD is an inflamed state. In an inflammatory milieu, hepcidin production increases. The hepatic iron-regulatory hormone Hepcidin and its receptor, the cellular iron exporter Ferroportin, form a feedback-regulated mechanism that maintains adequate plasma iron-transferrin concentrations for erythropoiesis and other functions, ensures sufficient iron stores, and prevents iron toxicity. In chronic kidney disease, inflammation and impaired renal clearance increase plasma hepcidin, which inhibits duodenal iron absorption and sequesters iron in macrophages. These hepcidin effects can cause systemic iron deficiency, reduced iron availability for erythropoiesis, and resistance to endogenous and exogenous erythropoietin.
Choice C: Correct option. Refer to the explanation for option B. He had pain and swelling of his right great toe; a foot doctor saw him, a bone scan was done and subsequently, ly the amputation. All findings suggest an infective etiology, probably osteomyelitis. There is a temporal relationship between the patient's anemia and an underlying chronic inflammatory state.
The high ferritin also suggests an inflammatory state.
Choice D: Incorrect option. Pure red cell aplasia, a form of severe ESA hypo-responsiveness mediated by anti-erythropoietin antibodies, was first reported with certain formulations of Epoetin alfa but has now been reported with all commercially available forms of ESA. This syndrome presents with rapid-onset severe anemia (hemoglobin <7 gg/dL, severe reticulocytopenia (reticulocyte count <10,000/l L, and marked elevations in serum ferritin (>1000 ng/mmL and transferrin saturation (>70%) due to low iron utilization. Pure red cell aplasia is unlikely given the absence of characteristic laboratory findings. Moreover, the patient did not receive Epoetin alfa.
Choice E: Incorrect option.Under-dialysis leads to anemia through the same mechanism mentioned earlier in option B. Under-dialysis worsens the uremic milieu, which in turn leads to an inflammatory state. The patient in this clinical vignette has been dialysed appropriatel is weekly Kt/V is 1.9, which is above the target goal of 1.7
Copyright © ABIM Exam World
Created On: 10/22/2018
Last Modified: 10/16/2026
50-year-old female patient whose group B is being evaluated for kidney transplant surgery. She had ESRD secondary to analgesic nephropathy and has been on hemodialysis for the last 5 years. She has had multiple sensitization events in the form of 3 pregnancies and several blood transfusions. Her current calculated PRA against class I antigen is 97% and against class II antigen is 99%. She has been enrolled in the national highly sensitized recipient program.
Her husband, who is blood group matched, came forward as a potential kidney donor, but she had a positive flowB andT-cell crossmatch against him. Single antigen bead assay demonstrated donor-specific antibodies against class II across DQB*15 and DPB*14. This transplant did not materialize as the patient declined the desensitization protocol. Now her younger brother comes forward as a potential donor. He is blood group A, and the flow B and T-cell crossmatch is negative, with no demonstrable donor-specific antibodies against this donor. The patient wants to know more about ABO-incompatible transplant.
Which of the following statements about the ABO incompatible transplant is correct?
| A. Three-year graft survival is inferior to blood group compatible transplants. | |
| B. The infectious and bleeding complications post ABOI kidney transplant are the same as blood matched kidney transplant. | |
|
|
C. All patients undergoing ABOI transplant need to undergo desensitization using IVIg, Plasma exchange, Rituximab irrespective of their donor/recipient pair Anti ABO titers for optimal outcomes. |
|
|
D. C4d staining on protocol biopsies is common feature and does not necessarily mean an antibody mediated rejection process in the absence of allograft dysfunction. |
|
|
Correct answer: Option D: C4d staining on protocol biopsies is a common feature and does not necessarily mean an antibody-mediated rejection process.
Explanation:
Choice A: Three-year graft survival is inferior to blood group-compatible transplants is incorrect. A comprehensive database analysis of 1420 ABOI living donor (LD) kidney transplants performed in 101 centers from 2005 to 2012 compared graft and patient survival with a matched cohort of ABO-compatible transplant recipients. Three-year graft and patient survival were ultimately identical. 1
Choice B: The infectious and bleeding complications post ABOI kidney transplant are the same as in blood-matched kidney transplant is also incorrect. Using USRDS and Medicare data from 2000–2007, 119 ABOI (non-A2 donor) transplant recipients were identified. Compared with ABO-compatible recipients, the risks of infectious and hemorrhagic complications were significantly higher, with a 2.2-fold higher risk of pneumonia, a 3.5-fold higher risk of wound infections, a 56% higher risk of pyelonephritis, and a nearly 2- fold higher risk of hemorrhage 2
Choice C: All patients undergoing ABOI transplant need to undergo desensitization using IVIg, Plasma exchange, Rituximab irrespective of their donor/recipient pair. Anti-ABO titers for optimal outcomes is also an incorrect answer. Historically, ABOI transplantation has been successful when performed after desensitization with plasmapheresis, intravenous Ig (IVIG), rituximab, and/or splenectomy to achieve ABO IgG antibody titersof 1:4. A recent publication demonstrated that these intensified treatments might not be necessary in donor/recipient pairs who have low-to-moderate titer ABO incompatibility 3
Choice D: C4d staining on protocol biopsies is a common feature and does not necessarily mean an antibody-mediated rejection process; in the absence of allograft dysfunction, this is the correct answer. C4d staining is not an uncommon feature seen in the protocol biopsies done in ABOI kidney transplant recipients. In the absence of allograft dysfunction, C4d staining has no clinical relevance and is part of graft accommodation.
Copyright © ABIM Exam World
Created On: 10/30/2018
Last Modified: 10/16/2026
A 28-year-old Caucasian gentleman comes to the clinic for a follow-up visit. He has been found to have type 1 diabetes mellitus since the age of 12 years. His cousin has the same disease. He reports no symptoms and uses an insulin pump with insulin aspart. He monitors blood sugar with a flash glucose monitor and uses carbohydrate counting for boluses. He reports infrequent hypoglycemic episodes, particularly 2 hours post-lunch, but manages them by himself. He exercises at least 60 minutes per day. His vitals show BP of 118/6 mmHg. His BMI i 23.2. Physical examination is unremarkable.
His laboratory investigations are reported as follows.
Characteristic | Value |
Hemoglobin | 14.2 gm/L |
WBC count | 6.8 X 10³/cubic mm |
Platelet count | 241 X 103/cubic mm |
Segmented Neutrophils Lymphocytes Monocytes Band neutrophils Eosinophils Basophils | 60% 36% 2% 0% 2% 0% |
Sr Sodium | 139 mEq/L |
Sr Potassium | 4.4 mEq/L |
Sr Creatinine | 0.6 mg/dL |
eGFR using CKD-EPI | 136.8 ml/min/1.73m2 |
Sr Bicarbonate | 24 mEq/L |
Sr Chloride | 101 mEq/L |
Total Bilirubin | 1.0 mg /dL |
AST | 16 U/L |
ALT | 18 U/L |
Sr Albumin | 4.0 g/dL |
HBA1C | 7.9% |
Sr Calcium | 10 mg/dL |
Urine dipstick | pH- 5.4 Albumin-nil no blood no WBCs |
24-hour urinary protein | 76 milligrams/day |
What is the MOST LIKELY incorrect statement regarding the hyperfiltration stage of Diabetic Kidney Disease in this patient?
| A. Renal hyperfiltration is usually diagnosed when the GFR is more than 120 ml/min,which corresponds to a renal function that exceeds two standard deviation above mean GFR. | |
| B. Renal hyper filtration usually precedes microalbuminuria in type 1 diabetes mellitus. | |
|
|
C. Renal hyper filtration is considered as a risk factor for future progression to chronic kidney disease (CKD) and end stage renal disease (ESRD) in type 1 DM. |
|
|
D. eGFR equations like MDRD equation can be used predict hyper filtration. |
|
|
The Correct Answer is Option D: eGFR equations like the MDRD equation can be used pto redict hhyperfiltration
Explanation:
Supraphysiologic elevation in GFR is observed early in the natural history of type 1 and type 2 diabetes mellitus and is due to glomerular hyperfiltration. Pathogenesis of hyperfiltration in diabetes is complex, with a prominent role for hyperglycemia and altered insulin levels, especially in early diabetes and prediabetes. Dilatation of the afferent (pre-capillary) glomerular arteriole plays an important role in the hyperfiltration response, by raising both the intra-glomerular pressure and renal blood flow.
Direct measurement of GFR is usually required to detect hyperfiltration because estimation equations, such as the Modification of Diet in Renal Disease (MDRD), usually underestimate the true GFR when it is normal or above normal.
Option A: A definite GFR cutoff is lacking. However, renal hyperfiltration is typically defined as a GFR between 120 mL/min and 150 mL/min/1.73 m2, or greater than 2 standard deviations above the mean GFR in normal, healthy individuals.
Option B: Hyperfiltration in diabetes precedes the onset of albuminuria and/or decline in renal function, and predisposes to progressive nephron damage by increasing glomerular hydraulic pressure
Option C: Hyperfiltration per se does not seem to fully explain adverse renal outcome, as the risk for ESRD in transplant donors is very low. However, in type 1 diabetes, rapid GFR decline is associated with renal hyperfiltration and impaired GFR and may predict progressive DKD before loss of renal function.
Copyright © ABIM Exam World
Created On: 10/30/2018
Last Modified: 10/16/2026
A 19-year-old African American woman comes to the clinic for a follow-up visit. She has been found to have type 1 diabetes mellitus since the age of 12. She has been using an insulin pump for the last 5 years. She reports no hypoglycemic symptoms and has been monitoring blood sugar with a flash glucose monitor. She reports infrequent hypoglycemic episodes, all of which are self-managed. She met with an ophthalmologist for eye screening and has no retinopathy. She exercises regularly for 30 mins. Her vitals show BP 127/66 mmHg. Her BMI is 22.2. Systemic examination is unremarkable.
Her laboratory investigations are as follows.
Characteristic | value |
Hemoglobin | 13.2 gm/L |
WBC count | 7.8 X 10³/cubic mm |
Platelet count | 241 X 103/cubic mm |
Segmented Neutrophils Lymphocytes Monocytes Band neutrophils Eosinophils Basophils | 60% 36% 2% 0% 2% 0% |
Sr. Sodium | 136 mEq/L |
Sr. Potassium | 4.2 mEq/L |
Sr. Creatinine | 0.6 mg/dL |
eGFR using CKD-EPI | 153.1 ml/min/1.73m2 |
Sr. Bicarbonate | 24 mEq/L |
Sr. Chloride | 101 mEq/L |
Total Bilirubin | 1.0 mg /dL |
AST | 16 U/L |
ALT | 18 U/L |
Sr. Albumin | 4.0 g/dL |
HBA1C | 8.2% |
Sr. Calcium | 10 mg/dL |
Urine dipstick | pH- 5.4 Albumin-nil no blood no WBCs |
24-hour urinary protein | 86 milligrams/day |
What is the MOST LIKELY False statement regarding the renal hyperfiltration stage of Diabetic Kidney Disease in this patient?
| A. Renal hyper filtration is attenuated by SGLT2 inhibition. | |
| B. Renal hyper filtration occurs in both type 1 and type 2 diabetes mellitus. | |
| C. Obesity can also lead to single-nephron hyper filtration. | |
|
|
D. Incretins like GLP-1 and GIP are neutral in terms of altering renal hemodynamics unlike SGLT2 blockers. |
|
|
The Correct Answer is Option D: Incretins like GLP-1 and GIP do not alter renal hemodynamics, unlike SGLT2 blockers.
Supraphysiologic elevation in GFR occurs early in the natural history of type 1 and type 2 diabetes mellitus due to glomerular hyperfiltration. Pathogenesis of hyperfiltration in diabetes is complex, with a prominent role for hyperglycemia and distorted insulin levels, especially in early diabetes and pre-diabetes. Dilatation of the afferent (pre-capillary) glomerular arteriole plays an important role in the hyperfiltration response, by raising both the intra-glomerular pressure and renal blood flow.
The effects of incretins can be demonstrated experimentally using GLP-1 receptor agonists (GLP-1RAs) and dipeptidyl peptidase (DPP) -4 inhibitors, which are associated with renal hemodynamic effects beyond glycemic control. These observations have been attributed to GLP-1–mediated inhibition of NHE3 (which assembles with DPP-4 in the proximal tubular brush border), reducing proximal sodium reabsorption and activating TGF (tubuloglomerular feedback).
Option A: In an 8-week study, empagliflozin in T1DM patients with whole-kidney hyperfiltration (mean GFR 172±23 ml/min per 1.73 m2) demonstrated a glucose-independent 19%decrease in GFR, which was associated with a decline in ERPF (estimated renal plasma flow) and estimated glomerular pressure and an increase in afferent arteriolar resistance, as assessed by the Gomez equations. SGLT2 inhibition could reduce (single-nephron) hyperfiltration in diabetes by restoring sodium-chloride concentration at the macula densa and subsequent TGF-mediated afferent arteriolar vasoconstriction.
Option B: Reported prevalence of hyperfiltration at the whole-kidney level varies greatly between 10% and 67% in type 1 diabetes mellitus (T1DM) (with GFR values up to 162 ml/min per 1.73 m2), and 6%–73% in patients with type 2 diabetes (T2DM) (up to 166 ml/min per 1.73 m2).
Option C: Independent of diabetes and glucose levels, body weight also augments GFR (by about 15% in obese to about 56% in severely obese non-diabetic subjects).
Copyright © ABIM Exam World
Created On: 10/31/2018
Last Modified: 10/16/2026
A 68-year-old Caucasian gentleman comes to the clinic for a follow-up visit. He is known to
have type 2 diabetes mellitus for the past 18 years. His father had diabetes from age 40 and developed kidney disease requiring dialysis after 15 years
of diabetes. He reports no symptoms. He has had hypertension and
coronary artery disease with a history of PCI 2 years ago. He has
non-proliferative diabetic retinopathy. His medications are sitagliptin,
gliclazide and metformin, in addition to losartan and hydrochlorothiazide. He
monitors blood sugar at home and reports no hypoglycemia. He
exercises at least 30 minutes per day. His vitals recording shows BP
of 68/66 mm Hg. His BMI is 29.2. Systemic examination is unremarkable.
His laboratory investigations are as follows.
Characteristic | value |
Hemoglobin | 12.2 gm/L |
WBC count | 6.8 X 10³/cubic mm |
Platelet count | 241 X 103/cubic mm |
Segmented Neutrophils Lymphocytes Monocytes Band neutrophils Eosinophils Basophils | 60% 36% 2% 0% 2% 0% |
Sr. Sodium | 139 mEq/L |
Sr. Potassium | 4.9 mEq/L |
Sr. Creatinine | 1.2 mg/dL |
Sr. Bicarbonate | 22 mEq/L |
Sr. Chloride | 101 mEq/L |
Total Bilirubin | 1.0 mg /dL |
AST | 16 U/L |
ALT | 18 U/L |
Sr. Albumin | 4.0 g/dL |
HBA1C | 7.8% |
Sr. Calcium | 10 mg/dL |
Urine dipstick | pH- 5.4 Albumin-trace no blood no WBCs |
24-hour urinary albumin | 200 milligrams/day |
What is the MOST LIKELY correct statement regarding the clinical diagnosis of Diabetic Kidney Disease in this patient?
|
|
A. Diabetic Kidney Disease previously called as diabetic nephropathy can be diagnosed clinically with renal biopsy only. |
| B. Presence of microalbuminuria is adequate for clinical diagnosis of Diabetic Kidney Disease. | |
| C. Presence of hematuria without non-diabetic kidney disease is impossible in Diabetic Kidney Disease as diabetic kidney disease is a non-proliferative glomerular disease. | |
|
|
D. Family history of Diabetic Kidney Disease is associated with renal involvement in Diabetes. |
|
|
The Correct Answer is
Option D: Family history of Diabetic Kidney Disease is associated with renal
involvement in Diabetes.
Familial studies have demonstrated clustering of diabetic nephropathy. Patients with DM who have a first-degree relative with T1/T2DM and diabetic nephropathy have a higher risk of developing diabetic nephropathy than those without an affected relative. This familial clustering has also been well documented in the Pima Indian population. Candidate genes include glucose transporter 2 (GLUT2), transforming growth factor beta (TGF-?, and endothelial nitric oxide synthase (eNOS).
Option A: Diabetic nephropathy is a clinical syndrome characterized by the following:
·
Persistent
albuminuria (>300 mg/d) that is confirmed on at least 2 occasions 3-6 months
apart
·
Progressive
decline in the glomerular filtration rate (GFR)
·
Elevated
arterial blood pressure
Option C: Microhematuria has been demonstrated in biopsy studies with isolated diabetic nephropathy. Red blood cell casts have also been described in patients with diabetic nephropathy. However, it is important to rule out other glomerular and extra-glomerular causes of hematuria.
Copyright © ABIM Exam World
Created On: 10/31/2018
Last Modified: 10/16/2026
A 30-year-old man was on hemodialysis for 6 months. He was an IV drug user and was diagnosed with HIV. His elder sister came forward as a potential kidney donor for him. He underwent a successful kidney transplant. Which of the following statements is true regarding kidney transplantation in HIV positive individuals and acute rejection episodes?
|
|
A. The episodes of acute rejection are more in HIV positive individuals compared to non-HIV positive patients. |
| B. The episodes of acute rejection are same in HIV positive individuals when compared to age and disease matched non-HIV counterparts. | |
| C. Cyclosporine is a preferred CNI as it has some invitro antiviral properties. | |
| D. There is a documented interaction between CNI and integrase inhibitors. Integrase inhibitors increase the CNI level. | |
| E. There is a proven benefit of using rATG for induction immunosuppression over anti IL-2 therapy to prevent rejections. |
|
|
Correct Answer. Option A. The episodes of acute rejection are more common in HIV positive individuals compared to non-HIV-positive patients.
Explanation.
Kidney transplant recipients with HIV have a high frequency of rejection. In a large, multicenter trial, one- and three-year rejection rates were 31% and 41%, respectively, compared with an expected one-year rejection rate of 12%, as reported by SRTR for all kidney transplant recipients. At European transplant centers, where most patients are induced with interleukin (IL)-2 receptor antibodies, one-year acute rejection rates among recipients with HIV have ranged from 15 to 44 %.
The higher rate of rejection in recipients with HIV is likely multifactorial. Drug-drug interactions between calcineurin inhibitors (CNIs) and protease inhibitors (PIs) can reduce immunosuppressive drug exposure to subtherapeutic levels. Patients on a CNI and PI require nonstandard dosing schedules (i.e., every other or every third day), which can make adherence difficult. Furthermore, concomitant administration of a PI and CNI results in a 40 % lower area under the curve (AUC) for CNI exposure at the same CNI target level, leading clinicians to underdose patients taking both medications systematically. Many transplant physicians transition patients off PI-based regimens whenever possible to integrase inhibitor-based regimens, which avoid these drug-drug interactions and allow standard immunosuppression dosing.
HIV-infected transplant recipients, compared with HIV-negative recipients, have a higher risk of acute rejection and, therefore, would theoretically benefit from antibody induction therapy. However, given the underlying immunosuppressed state of HIV-infected patients, prolonged lymphocyte depletion with antibody induction therapy could potentially increase their risk of developing opportunistic infections. Some centers avoid the use of antibody induction therapy among HIV-infected transplant recipients. In centers that use antibody induction therapy, some use basiliximab (an IL-2 receptor antibody) based on data from two studies of HIV-infected kidney transplant recipients that demonstrated an increased risk of infection among those treated with rATG-Thymoglobulin. Other centers prefer to use rATG-Thymoglobulin given its superior efficacy in preventing acute rejection in HIV-negative recipients.
Copyright © ABIM Exam World
Created On: 05/12/2020
Last Modified: 10/12/2026
A 45-year-old female is waitlisted for a kidney transplant. Her native kidney disease is IgA nephropathy. Her blood group is B, and her CPRA is 90%. You are seeing her in the clinic as part of kidney transplant work. As part of documentation, you discuss with her the Public Health Service – Increased Risk Donors (PHS-IRD). You explain PHS-IRD and ask whether she consents. Your rationale for explaining this is the long wait time for blood group B in your allocation area, especially under CPRA 90%. Which of the following statements regarding the PHS-IRD is TRUE?
| A. As per the new guidelines there is no need to take an informed consent for PHS-IRD from the potential recipient. | |
|
|
B. PHS-IRD kidneys have a discard rate of 2.5-fold. |
| C. The kidney from PHS-IRD have an infection transmission risk anywhere between 10-15% depending on the type of infection. | |
| D. Recipient who received IRD kidneys have increased risk of death at 6 months compared to those who declined the offer. | |
|
|
E. There is increased risk of allograft loss in recipients of PHS-IRD kidneys. |
|
|
Correct Answer. Option B. PHS-IRD kidneys have a discard rate of 2.5-fold.
Explanation.
The United States Public Health Service (PHS) redefined donors who were previously classified by the Centers for Disease Control and Prevention as being at increased risk for transmission of hepatitis B virus (HBV), hepatitis C virus (HCV), and HIV. The number of deceased donors that are part of this classification has increased dramatically because of the opioid epidemic, comprising over 20% of donor kidneys. Overall, overdose-death donors accounted for 1.1% of organ donors in 2000 and 13.4% in 2017. Importantly, transplantation candidates and providers should be well versed in the very low risk of disease transmission from these donors, all significantly < 1% even under the highest-risk circumstances (intravenous drug overdose, syringe-on-person). Unfortunately, “PHS increased-risk donor” (IRD) status is independently associated with nearly 2.5-fold increased odds of turndown. An analysis by Bowring et al. used SRTR data from 104,998 kidney transplantation candidates who were offered IRD kidneys that were eventually accepted. The median KDPI of these kidneys was 30 (interquartile range, 16–49). Importantly, after 5 years, only 31.0% of candidates who declined IRDs received non-IRD DDKTs later; the median KDPI of these non-IRD kidneys was 52. Those who accepted an IRD had a substantially lower risk of death at 1 to 6 months after decision (aHR, 0.50; 95% CI, 0.67 to 0.90; P=0.006) and beyond 6 months after decision (aHR, 0.46; 95% CI, 0.52 to 0.58; P< 0.001). A single-center report of PHS-IRD kidney utilization reviewed offers made to 2423 kidney transplant candidates from June 2004 to May 2005; 1502 ultimately received a transplant with or without a PHS-IRD kidney. Accepting a PHS-IRD kidney offer was associated with lower mortality (3.63% versus 11.6%; aHR, 0.467; P = 0.0008) and a lower risk of allograft loss than in non–PHS–IRD recipients (P = 0.007), with no transmission of HCV, HBV, or HIV.

Copyright © ABIM Exam World
Created On: 05/12/2020
Last Modified: 10/12/2026
All the following drugs cause hyperkalemia. All the drugs act by a specific mechanism to induce hyperkalemia. Only one drug acts through a different mechanism. Which drug induces hyperkalemia via a different mechanism than the others?
|
|
A. Heparin. |
| B. Low molecular weight heparin. | |
| C. Aminoglutethimide. | |
| D. Dabigatran. | |
|
|
E. Calcineurin inhibitors. |
|
|
Correct Answer. Option D. Calcineurin inhibitors.
Explanation.
Heparin, low-molecular-weight heparin, Aminoglutethimide and Dabigatran all impair adrenal hormone metabolism. These drugs cause potent inhibition of adrenal hormone synthesis, leading to hyperkalemia.
The hyperkalemia seen with calcineurin inhibition is likely multifactorial and relates to inhibitory effects on Na+-K+-ATPase in collecting ducts and possibly to distal tubular acidosis. In addition, there is evidence that decreased numbers of mineralocorticoid receptors, which are detected in 75% of patients who are treated with cyclosporine, lead to hyperkalemia and metabolic acidosis as a result of aldosterone resistance. Recently, it was demonstrated that cyclosporine reduces paracellin-1 expression in thick ascending limb cells. This decrease in magnesium transport likely contributes to the magnesium wasting and hypomagnesemia induced by cyclosporine, which is associated with chronic interstitial fibrosis, faster declining kidney function, and increased rates of graft loss in renal transplant recipients with CNI nephrotoxicity. Finally, it was shown that cyclosporine indirectly opens ATP-sensitive K+ channels by inhibiting calcineurin, which could contribute to the CNI-associated hyperkalemia.
Copyright © ABIM Exam World
Created On: 05/18/2020
Last Modified: 10/12/2026
A 25-year-old man is referred to you for evaluation of nephrotic syndrome. A kidney biopsy is done, and it shows minimal change disease. His BP is 150/90 mmHg, and his heart rate is 70 bpm. His current medications are prednisone 40 mg once daily, furosemide 40 mg twice daily, Ramipril 10 mg once daily, and Calcium + vitamin D supplementation. Clinical exam shows raised JVD 3 + pitting edema to the right thigh. His blood work shows serum creatinine 0.9 mg/dL, BUN 35 mg/dL, and serum potassium 3.2 mEq/L. Urine analysis is bland, and his 24-hour urine protein is 5.8g. He is strictly following his salt restriction. After a month’s follow-up, his proteinuria has decreased to 4.0 g/24 hrs, but his foot edema remains unchanged. His serum albumin has improved from 1.9 g/L to 2.8 g/L. Which of the following drugs will benefit the patient?
| A. Metolazone. | |
| B. Amiloride. | |
| C. Chlorthalidone. | |
| D. Cyclophosphamide. | |
| E. Amlodipine. | |
| F. Losartan. |
|
|
Correct Answer. Option B. Amiloride.
Explanation.
Two major factors, both of which lead to retention, have been thought to be responsible for the development of edema in patients with nephrotic syndrome; both likely contribute to a variable degree in individual patients:
Distinguishing between these mechanisms is clinically important because it affects tolerance of diuretic therapy. Diuretics are well tolerated in patients with renal sodium retention but, if underfilling is the primary mechanism, can lead to worsening hypovolemia as evidenced clinically by an elevation in serum creatinine.
Studies in experimental animals with unilateral nephrotic syndrome or glomerulonephritis suggest that primary sodium retention in these disorders is due to increased sodium reabsorption in the collecting tubules, which is also the site of action of atrial natriuretic peptide (ANP) and the related renal hormone urodilatin. This is called the overfill hypothesis because primary renal sodium retention leads to volume expansion.
Increased activity of the epithelial sodium channel (ENaC) may contribute to sodium retention. Serine proteases are aberrantly filtered in nephrotic syndrome, increasing their concentration in the urine. Plasminogen (which is activated by epithelial urokinase-type plasminogen activator [uPA] to plasmin) in nephrotic urine may activate ENaC via proteolytic cleavage of the gamma chain, providing a potential mechanism by which filtered proteins cause sodium retention. It also explains the observation that remission from the nephrotic syndrome is generally preceded by a decrease in urinary protein excretion. In an animal model of nephrotic syndrome, mice treated with the serine protease inhibitor aprotinin normalized urinary serine protease activity and prevented sodium retention. A similar result was seen when rats with nephrosis were treated with the ENaC inhibitor amiloride.
Hence, amiloride is the best answer for this clinical vignette.
Copyright © ABIM Exam World
Created On: 05/18/2020
Last Modified: 10/12/2026
A 68-year-old Hispanic woman is referred to you for evaluation of nephrotic syndrome. She has a history of type 2 diabetes and hypertension. Both diabetes and hypertension are well controlled. Her serum creatinine is 2.1 mg/dL. Urinalysis shows only proteinuria, with a protein-to-creatinine ratio of 6. A renal biopsy shows amyloidosis and interstitial fibrosis. Based on the history, biopsy findings, and proteinuria above, which diagnostic test would you order to characterize the type of her amyloidosis?
| A. Electron microscopy of the glomerulus. | |
| B. Immunofluorescent studies. | |
| C. Immunofixation study. | |
|
|
D. Amyloidosis derived from leukocyte chemotactic factor 2 (ALECT 2). |
| E. No further testing. |
|
|
Correct Answer. Option D. Amyloidosis derived from leukocyte chemotactic factor 2 (ALECT2).
Explanation.
ALECT2 amyloidosis is a systemic form of amyloidosis with predominantly renal and liver involvement. Most reported cases in North America (88 to 92 %) occur in older Hispanic adults of Mexican origin. However,Punjabis, First Nations people in British Columbia, and Native Americans also have a predisposition for this disorder. In one study of renal amyloidosis among Egyptians, ALECT2 amyloidosis was the second most common form of renal amyloidosis behind AA and ahead of AL amyloidosis. Cases have also been reported in Pakistani, Sudanese, and Chinese patients. The pathogenesis of ALECT2 amyloidosis remains poorly understood. Patients typically present with chronic kidney disease (CKD) and variable proteinuria; nephrotic syndrome is uncommon. Diagnosis requires a kidney biopsy, preferably with laser microdissection and mass spectrometry. Patients with ALECT2 amyloidosis characteristically have diffuse Congo red-positive amyloid deposition in the cortical interstitium, with variable glomerular and vascular involvement. Overall, patients with ALECT2 amyloidosis have better survival than those with AL or AA amyloidosis, possibly because cardiac involvement is absent or rare. However, renal survival is relatively poor, with up to 39 percent of patients progressing to end-stage renal disease (ESRD). There are no specific therapies for ALECT2 amyloidosis.
Copyright © ABIM Exam World
Created On: 05/19/2020
Last Modified: 10/12/2026
A 50-year-old male is referred for evaluation of high-grade proteinuria. He does not have diabetes but is known to have hypertension. He takes hydrochlorothiazide 12.5 mg once daily for that. The blood and urine tests are shown below. You perform a kidney biopsy, and it shows focal segmental glomerulosclerosis (FSGS). The concern is whether this is primary vs. secondary FSGS. Which of the following options would be supportive of secondary FSGS as opposed to primary FSGS?
Value | Test |
11.2 gm/L. | Hemoglobin |
6,800 cells/cumm | WBC count |
2,41,000 cells/cumm | Platelet count |
139 mEq/L. | Sr. Sodium |
5.2 mEq/L. | Sr. Potassium |
1.6 mg/dL. | Sr. creatinine |
22 mEq/L. | Sr. Bicarbonate |
101 mEq/L. | Sr. Chloride |
4.0 g/dL. | Sr. Albumin |
10 mg/dL. | Sr. Calcium |
p: 5.4. Albumin-++++ No blood. No WBCs. | Urine |
3.8 grams/day.
| 24-hour urinary protein |
Negative
| ANCA |
Negative
| ANA |
No monoclonal proteins | Serum protein electrophoresis |
negative | HIV |
negative | HbsAg |
negative | Anti HCV |
| A. Increase in mesangial matrix. | |
| B. Focal sclerosis only in some parts of the glomerulus in primary FSGS. | |
|
|
C. Serum albumin and width of foot processes (effacement of foot processes). |
| D. Tram-tract appearance of the basement membrane. |
|
|
Correct Answer. Option C. Serum albumin and width of foot processes (effacement of foot processes).
Explanation.
The causes of FSGS may be primary (idiopathic) or secondary. Secondary forms are generally characterized by glomerular hyperfiltration and hypertrophy. It was suggested that serum albumin and the degree of foot processes effacement can distinguish primary from secondary forms of FSGS. Praga et al. reported that serum albumin levels are <3 g/dL in those with biopsy-proven primary FSGS, compared to
>3.5 g/dL in those patients with secondary FSGS. A histopathologic study by Deegens et al. showed that foot process width is significantly higher (3200 nm) in primary FSGS than in secondary FSGS (1098 nm; normal 562 nm). Overall, foot process width over 1500 nm differentiated idiopathic from secondary FSGS with high sensitivity and specificity. This suggests that patients with primary FSGS have complete effacement of foot processes, whereas secondary FSGS shows patchy effacement.
In a study of 46 patients with an FSGS lesion, patients were divided by the degree of foot process effacement observed on kidney biopsy. Patients were categorized as having diffuse (?80 %) or limited (<80 %) foot process effacement. Compared with patients with limited foot process effacement, those with diffuse foot process effacement without an identifiable cause had lower serum albumin levels and higher proteinuria and were more likely to have nephrotic syndrome on presentation (100 vs 4 %). Based upon these results, patients who presented with diffuse foot process effacement without an identifiable cause and nephrotic syndrome were classified as primary FSGS. Patients with segmental foot process effacement, with or without an identifiable cause, or diffuse foot process effacement due to an identifiable cause were classified as secondary FSGS.
Copyright © ABIM Exam World
Created On: 05/19/2020
Last Modified: 10/12/2026
All of the following help predict AV Graft stenosis EXCEPT:
| A. Hyperpulsatility of the AV Graft | |
| B. Reduced pulse augmentation | |
| C. Increased bleeding and clots | |
| D. Decreased KT/V | |
| E. Decreased Blood Flow rate | |
|
|
F. Surveillance of the graft |
|
|
Copyright © ABIM Exam World
Created On: 09/23/2020
Last Modified: 10/12/2026
A 20-year-old male was at a party where, after dancing, he ate a lot of cake because it was “delicious”. After 2-3 hours, he developed a sudden onset of weakness in all 4 limbs. He has had two similar episodes before. He was rushed to the nearest ER. On examination: P: 88/min, BP: 140/96 mm Hg, Pallor+, no thyroid enlargement. He is alert and oriented. No cranial nerve involvement or neck muscle weakness. Motor power is grade 2-3 in all extremities, reflexes sluggish to absent. Sensory exam is normal. Laboratory results reveal the following:
pH 7.4
pCO2 40 mm Hg
PaO2 98 mm Hg
HCO3 24 mEq/L
O2 saturation 98%
Na 140 mEq/L
K 2.2 mEq/L
Cl 103 mEq/
BUN 10 mg/dl
S.Cr 0.8 mg%
S. Ca 10.2 mg/dl
PO4 2.5 mg/dl
Mg 2.2 mg/dl
Urine Electrolytes
Urine Na 100 mEq/L
Urine K 15 mEq/L
Which of the following is the MOST likely diagnosis?
|
|
A. Familial periodic paralysis. |
| B. Renal tubular acidosis | |
| C. Primary hyperaldosternism. | |
| D. Thyrotoxic periodic paralysis |
|
|
Copyright © ABIM Exam World
Created On: 09/12/2017
Last Modified: 10/17/2026
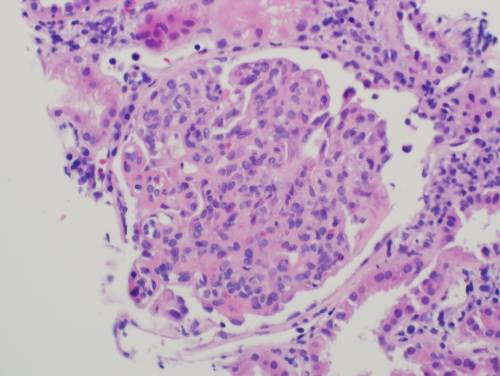
A 35-year-old Caucasian male presents with persistent swelling of both legs associated with dark colored urine for two months. He went to an emergency room 2 months ago for these complaints and was told that he has some protein and blood in the urine. He was treated with levofloxacin for 3 days. There is no other past medical history. No history of skin rash or joint swelling. On examination,n the blood pressure was 130/85 mm H,g and there was bilateral 1+ pedal edema. The rest of the physical examination was normal. Urine analysis showed 3+ proteinuria, 10-15 RBCs per high-power field, and occasional RBC casts. BUN was 10 mg/dL, and serum creatinine was 0.9 mg/dL. Antistreptolysin was negative; C3 was decreased, and C4 was normal. Antinuclear antibodies, ANCA, hepatitis B and C serology were negative. 24-hour urine collection showed 2 g proteinuria, and a kidney biopsy was performed. Light microscopy showed increased mesangial matrix and cellularity, and the glomerular basement membrane appeared irregularly thickened. Silver stain revealed duplication of the glomerular basement membrane in multiple glomeruli. Immunofluorescence showed positive staining for C3, but negative for IgG, IgM and IgA. Electron microscopy revealed electron-dense deposits in the mesangium and subendothelial area.
What is the most likely diagnosis?
| A. Acute poststreptococcal glomerular nephritis | |
| B. Diffuse proliferative lupus nephritis | |
| C. Dense deposit disease | |
|
|
D. C3 glomerulopathy |
| E. |
|
|
Copyright © ABIM Exam World
Created On: 09/12/2017
Last Modified: 10/13/2026
A 25-year-old male comes to the physician complaining of flank pain and hematuria. He says the pain is constant and dull. There is no frequency, urgency or dysuria. He has a history of mental retardation and seizures. On physical exam, his blood pressure is 140/90 mm Hg, and his pulse is 80 bpm. He has multiple yellow papules on his nose and cheeks and numerous blanche, skin-colored spots on his face. A 2-3 cm hypopigmented macule is noted on the right arm. CT scan of the head was done as the patient presented with seizures. CT head was reported normal. CT scan of the abdomen shows bilateral hypodense fat-containing renal masses and cysts.
What is the MOST likely diagnosis associated with these findings?
| A. Von Hippel Lindau | |
| B. Sturge Weber Syndrome | |
|
|
C. Tuberous Sclerosis |
| D. Osler Weber Rendu | |
| E. Neurofibromatosis type 2 |
|
|
Copyright © ABIM Exam World
Created On: 09/13/2017
Last Modified: 10/17/2026
A 15-year-old boy is brought to the ER by his foster mother, who states that when she got home from work, she noticed he was acting very strange. He had slurred speech and seemed confused. He appeared very uncoordinated, and she was unsure whether he had fallen or hit his head. She states that he is somewhat a troubled boy but doesn’t know much about his history, as he has been in and out of the foster care system out of state. On physical exam, he is tachycardic and has tachypnoea. Pupils are dilated, but there is no nystagmus. Fundoscopy shows hyperemia of the optic disc is relatively uncooperative but not aggressive or hostile. When asked about suicidal thoughts, he responds only with inaudible mumbling. His foster mother left for work 10 hours prior and assumed he left for school. She is unsure when these symptoms began or what may have triggered them. P is 105/ min, BP is 140/90 mm Hg, RR is 28/min, and T is 97.1 F. Laboratory examination is as follows:
Na 135 mEq/L
K 5.0 mEq/L
CL 105 mEq/L
BUN 19 mg/dL
Cr 1.3 mg/dL
HCO3 8 mEq/L
Glucose 100 mg/dL
pH 7.3
pO2 90 mmHg
pCO2 22 mmHg
Measured serum osmolarity: 320 mmol/L
What is the next step in management?
| A. Gastric lavage | |
| B. N-acetylcystiene and activated charcoal | |
| C. Fomepizole | |
|
|
D. Fomepizole and Hemodialysis |
|
|
E. Obtain serum levels of salycylate, methanol and ethylene glycol levels |
|
|
Copyright © ABIM Exam World
Created On: 09/13/2017
Last Modified: 10/17/2026
All of the following help predict AV Graft stenosis EXCEPT:
|
|
A. Hyperpulsatility of the AV Graft |
| B. Ruduced pulse augmentation | |
| C. Increased bleeding and clots | |
| D. Decreased KT/V | |
| E. Decreased Blood Flow rate | |
|
|
F. Surveillance of the graft |
|
|
Copyright © ABIM Exam World
Created On: 09/14/2017
Last Modified: 10/17/2026
A 40-year-old pleasant African man with ESRD secondary to FSGS started automated peritoneal dialysis. His prescription includes 2.5 L and 3 exchanges over 8 hours at night, with a last fill of 2 L. His urine output is 1000 mL/day. Typical ultrafiltration on the cycler is 1000 mL. The average drain volume during the day dwell was 1500 mL before going on the cycler at night.
He came with complaints of lower abdominal wall edema extending to the scrotum over the past 5 days. Without any change in the dialysis prescription, his drain volume before going on the cycler dropped to 900 mL, and the ultrafiltration volume on the cycler came down to 100 mL. He reports no pain with fill or drain.
What is the next step?
| A. Chest X ray PA and lateral view | |
| B. Drain the fluid middle of the day to reduce the dwell time | |
| C. PD catheter manipulation | |
|
|
D. Abdominal CT scan with contrast in the dialysate |
| E. Switch to hemodialysis | |
| F. Pleurodesis |
|
|
Copyright © ABIM Exam World
Created On: 09/14/2017
Last Modified: 10/17/2026
Cyclosporine nephrotoxicity in a renal transplant recipient is associated with all of the following renal biopsy findings EXCEPT:
(THIS PICTURE BELOW IN LOW POWER SHOWS ONE OF THE CLASSICAL FINDINGS IN CSA TOXICITY)

| A. Interstitial Fibrosis | |
| B. Tubular atrophy | |
| C. Endothelial cell swelling | |
|
|
D. Glomerular thrombin deposits |
| E. Glomerular basement membrane thickening | |
|
|
F. Double contours of the GB |
|
|

Copyright © ABIM Exam World
Created On: 09/14/2017
Last Modified: 10/17/2026
A 68-year-old African American male with a known history of diabetes mellitus, hyperlipidemia, CVD, and GERD presents to the ER with chest pain and shortness of breath. The patient says the pain is crushing and radiates to his left arm. It woke him from sleep 30 minutes ago. He took his antacids and 4 tablets of nitroglycerin, and the pain got better. His current medications include low-dose aspirin, metoprolol, glyburide, pioglitazone, lisinopril, simvastatin, and omeprazole. He recently suffered an upper respiratory infection for which he was given Levofloxacin. Vitals: BP 160/95 mm Hg, T 98.1, HR 110. He has no leg edema and no jugular venous distention. EKG shows LVH by voltage criteria with an isoelectric ST segment. Serial troponin levels are normal. A stress test showed evidence of stress-induced ischemia in the anterior leads. He is scheduled for cardiac catheterization the next day. Laboratory results are as follows:
Serum Chemistry:
Na 143 mEq/L
K 3.5 mEq/L
Cl 101 mEq/L
HCO3 22 mEq/L
BUN 35 mg/dL
Cr 3.0 mg/dL
Glucose 110 mg/dL
What would you do to PROTECT the kidneys before doing the cardiac catheterization?
| A. Dopamine IV infusion before and after the procedure. | |
| B. Nifedipine. | |
|
|
C. Isotonic sodium bicarbonate infusion before and after the procedure. |
| D. N Acetyl Cysteine before and after the procedure | |
| E. Start mannitol IV before the procedure | |
| F. Left ventriculogram quickly with coronary angiogram |
|
|
Copyright © ABIM Exam World
Created On: 09/14/2017
Last Modified: 10/17/2026
As per the JNC VIII committee recommendation, for individuals who are part of the African American population, including those with diabetes, the initial treatment should include a thiazide-type diuretic or calcium channel blocker (CCB).
Which of the following thiazide-type diuretics is preferred as the initial antihypertensive therapy?
| A. Hydrochlorthiazide | |
|
|
B. Chlorthalidone |
| C. Indapamide | |
| D. Metalazone | |
| E. Polythiazide |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
Which of the following antihypertensive medications resulted in better blood pressure control and cardiovascular outcomes when combined with an ACE inhibitor?
| A. Beta blocker | |
|
|
B. Calcium channel blocker |
| C. Angiotensin Receptor Blocker | |
| D. Diuretics |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
The ACCOMPLISH trial is the first major trial addressing the issue of combination therapy in 11,506 patients who were at high cardiovascular risk. The goal blood pressure was <130/80 mm Hg in patients with diabetes or impaired renal function, and <140/90 mm Hg in patients with prior cardiovascular disease.
Which of the following combinations of blood pressure medications was the best in reducing cardiovascular events and slowing the progression of nephropathy in patients with hypertension who were at high risk for such events?
| A. ACEI + Diuretics | |
|
|
B. ACEI + CCB |
| C. ACEI + Beta-blocker | |
| D. CCB + Beta-blocker |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
An 18-year-old male is brought to the renal clinic for evaluation of hypertension. There is no history of edema of the feet, puffiness of the face, hematuria, oliguria or recurrent urinary tract infections. He is an active football player, but lately he complains of weakness and muscle cramps. His blood pressure for the last 3-4 years has always been borderline high and during this visit was as noted below.
Physical examination shows: Pulse 100/min; all peripheral pulses are well felt. BP 150/100 mm Hg, Temp. 37.4 degrees C. He is pale. His growth is stunted. His cognitive function is normal, and no focal neurological deficits are noted. Other systems are unremarkable. Laboratory examination is as follows:
Hemoglobin 13.5 g/dL
Hematocrit 42%
Platelet Count 150,000 mm3
White Blood Cells 8,000 mm3
Urinalysis:
Protein 100 mg/24 h
Glucose None
Red Blood Cells None
White Blood Cells None
Leukocyte Esterase Negative
Nitrites Negative
Chemistry:
BUN 13.5 mg/dL
Creatinine 0.9 mg/dL
Sodium 140 mEq/L
Potassium 5.8 mEq/L
Bicarbonate 18.5 mEq/L
Chloride 112 mEq/l
Calcium 9.2 mEq/L
Phosphorus 3.2 mg/dL
Aldosterone 5 ng/mL
PRA <1.0 ng/dL/hr
Glucose 100 mg/dL
HbA1C 5.30%
S. Osmolality 282 mOsmol
Uric Acid 5.3 mg/dL
ESR 9.8 mm/h
ABG:
pH 7.25
PCO2 32 mm Hg
HCO3 16 mEq/L
PO2 90 mm Hg
U: NNormal-sizedkidneys, no hydronephrosis
Considering the history and the laboratory findings, which of the following is most likely the cause of hypertension in this patient?
| A. Liddle's Syndrome | |
|
|
B. Gordon's Syndrome |
| C. Congenital adrenal hyperplasia | |
| D. Glucocorticoid-remediable aldosteronism | |
| E. Mineralocorticoid receptor activating mutation |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
A 56-year-old male was brought to the emergency room with drowsiness and lethargy. He has had these symptoms for the past 2 days. He complains of a recent history of anorexia, nausea, and vomiting. He has diabetes mellitus and has been on glimepiride 1 mg daily for the last 4 years. One week ago, he had decreased vision with redness in his right eye. He was treated by his ophthalmologist with drops,s which seem to have resolved the problem. He currently takes cholecalciferol weekly for osteoporosis. On physical examination, his pulse is 80/min, blood pressure is 140/90 mm Hg, respiratory rate is 20/min, and temperature is 97.7°F. The patient appears drowsy but shows no focal neurological deficits. Review of systems is otherwise unremarkable. Urinalysis is positive for glucose and negative for proteinuria, WBCs and RBC casts. A24-hour urinary protein collection shows proteinuria of 3.5 g/day. Further labs reveal:
Hemoglobin 8 gm%
Hct 24%
MCV 85
WBC 7800/ml
PMN 80%
Lymphocytes 20%
ESR 80 mm/hr
Na 145 mEq/L
BUN 80 mg/dL
Cr 1.8 mg/dL
CL 115 mEq/L
HCO3 25 mEq/L
Uric acid 5.8 mg/dL
Ca 14 mg/dl
PO4 2.8 mg/dL
Total Protein 7.8 gm/dL
Albumin 3.5 mg/dL.
Vitamin D 40 ng/ml
PTH 10 pg/ml
Which of the following is most likely the cause of his hypercalcemia?
| A. Vitamin D toxicity | |
| B. Primary hyperparathyroidism | |
|
|
C. Multiple myeloma. |
| D. Sarcoidosis |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
A 25-year-old female is referred by her primary care provider for evaluation of hypertension and hypokalemia. Her primary care provider has already started her on oral potassium despite a potassium level of 2.8 mEq/L. Despite amlodipine and lisinopril, her blood pressure is 154/96 mm Hg. There is no renal bruit. Systemic and fundus examinations are normal. Her mother was also diagnosed with hypertension at an early age. Her brother died of a cerebrovascular accident 2 years ago. Laboratory findings are as follows:
Na 140
Potassium 2.8
Chloride 100
HCO3 26
BUN 15
Creatinine 0.8
Glucose 110
TSH and Cortisol are normal
ACTH elevated
Renin 0.7 (Low)
Aldosterone 48 (elevated)
Urinalysis:
Sodium 240 mEq/D
Potassium 98 mEq/D
Urinary 18-OH Cortisol and 18-oxocortisol are elevated.
The most appropriate treatment for this patient is:
| A. Steroids | |
| B. Spironolactone | |
|
|
C. Steroids + Spironolactone |
| D. Amiloride |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
A 60-year-old with recently diagnosed colon cancer and diabetes presents with bilateral pedal edema; BP is 120/80 mm Hg. Urinalysis showed 4+ protein, no RBCs or WBCs, and 8-10 Hyaline casts. His BUN is 20, Creatinine is 1 mg/dL, and albumin is 2 grams/dL. A 24-hour urine collection showed 10 grams of protein. The patient undergoes a kidney biopsy. The EM is shown below :

What is the most likely diagnosis?
| A. Crescentic GN | |
| B. IgA nephropathy | |
| C. Minimal change disease | |
| D. Focal segmental glomeruloscerosis | |
|
|
E. Membranous nephropathy |
| F. Diabetic nephropathy |
|
|
The correct answer is E
Membranous Nephropathy.
Electron microscopy shows subepithelial electron-dense deposits, as classically seen in membranous nephropathy. If in the question there is a suggestion of colon, breast, or lung cancer, then the glomerulopathy is usually membranous. Then look for other histopathological findings that confirm the diagnosis: subepithelial electron-dense deposits.
Explanation:
BOARD POINT - FAMILIARIZE YOURSELF WITH THESE ASSOCIATIONS :
1. Solid cancers (colon, breast, lung, renal) plus proteinuria = Membranous nephropathy
2. Hodgkin's lymphoma plus proteinuria = Minimal change disease
3. HIV plus proteinuria = Focal segment glomerulosclerosis FSGS
4. Pamidronate plus protenuria = FSGS (rare)
5. Myeloma, no albuminuria on dipstick, but proteinuria on protein/creatinine ratio or 24-hour urine: Light chain nephropathy
6. Myeloma with nonspecific proteinuria (on dipstick, urine protein/creatinine ratio and 24-hour urine): Light chain nephropathy or amyloidosis.
BOARD POINT - FAMILIARIZE YOURSELF WITH THESE HISTOPATHOLOGY ASSOCIATIONS FOR VARIOUS GLOMERULAR DISEASES
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
You are the nephrologist on call. The ER calls you for an 18-year-old female who is complaining of vomiting and diarrhea. Her serum sodium is 116 mEq/L and Serum potassium is 5.9 mEq/L. On physical examination, the patient is drowsy; pulse is 126/min, BP is 90/60 mm Hg, and RR is 32/min. Her chest is clear. Her heart sounds are normal, with no murmur. The patient is drowsy but arousable, with no focal neurological deficit. Laboratory findings are as follows:
Hb 16 gm/dl
WBC 12,800/cmm
Polymorph 46%
Lymphocytes 16%
Eosinophils 4%
Monocytes 4%
Platelets 2,40,000/cmm.
CL 70 mEq/L
BUN 10 mg/dl
Creatinine 0.5 mg/dl
Na 116 mEq/L
K 5.8 mEq/L
Urinalysis:
pH 6.4
Protein trace
Glucose absent
Microscopic: occasional WBCs & RBCs
Urinary Na 90 mEq/L
Urinary K 20 mEq/L
ABG
PH 7.32
PCO2 36
HCO3 20 mEq/L
PaO2 92
O2 saturation 98%
S. Cortisol 6.00 mg/dl
TSH 3.5 IU/m (Normal 0-5 IU/m ).
Both plasma Renin and Aldosterone are high.
Which of the following conditions is most likely with these findings?
|
|
A. Type 4 RTA |
|
|
B. Pseudo-hypo-aldosteronism Type 1 |
| C. Gordon's syndrome | |
| D. Diarrhea |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
A 32-year-old male is brought to the renal clinic with a history of hematuria, oedema of the feet, and puffiness of the face. He reports fever and sore throat a week ago. He also complains of breathlessness on exertion and oliguria. Physical examination shows: Pulse 100/min, BP 150/100 mm Hg, and Temp. 37.4 C. He is pale. He has facial puffiness and oedema of the feet. Systemic examination-unremarkable. Laboratory examination is as follows:
Hb 10.5 g/d
Hct 34%
Platelet 250,000 mm3
WBC 8,000 mm3
Differential count: P 80% L 12% E 6% M 2%
ESR 9.8 mm/h
Urinalysis:
Protein 3000 mg/24 h
Glucose None
RBC 50-60/hpf Dysmorphic
WBC occasional
Leukocyte Esterase Negative
Nitrites Negative
BUN 40 mg/dL
Creatinine 3.9 mg/dL
Sodium 140 mEq/L
Potassium 4.2 mEq/L
Bicarbonate 25.5 mEq/L
S. protein 5.5 g/dl
S. Albumin 2.5 g/dl
Calcium 9.2 mEq/L
Phosphorus 3.2 mg/dL
Glucose 100 mg/dL
Uric Acid 5.3 mg/dL
C 3 Low
C4 normal
HBsAg /HIV Neg
ANA Neg
Kidney Biopsy: Shows enlarged Glomeruli, lobular accentuation, mesangial hypercellularity, endo-capillary proliferation and double contour along the capillary wall. IF shows bright C3 in the mesangium and capillary wall with absent immunoglobulin staining.
Electron Microscopy: Suggestive of dense deposits.
What is the BEST treatment option for this patient?
| A. Plasma exchange + Rituximab | |
| B. Rituximab | |
|
|
C. Eculuzimab |
| D. Cyclophosphamide + Steroids |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
A 36-year-old female was diagnosed with membranous nephropathy secondary to SLE. Her 24-hour protein excretion was 7.5 gms/day. Her serum creatinine was 0.9mg/dl. She was started on 500 mg of cyclophosphamide IV every 15 days (Euro-Lupus) and prednisolone 1 mg/kg orally per day. After 3 months of therapy, she presented with decreased urine output, puffiness of the face, and oedema of the feet. On physical examination, her temperature was 37 C, blood pressure 160/100 mm Hg, pulse 90/min, and respiratory rate 20/min. She is anemic, with facial puffiness and foot oedema. On systemic examination, air entry was decreased at both lung bases, and heart sounds were distant and feeble. Chest X-Ray reveals bilateral pleural effusions. Echocardiogram reveals mild to moderate pericardial effusion. Laboratory examination is as follows:
Hemoglobin 10.0 g/dL
Hematocrit 34%
Platelet Count 150,000 mm3
WBC 8,000 mm3
Differential count: T P 80% L 12% E 6% M 2%
ESR 50.8 mm/h
Urinalysis:
Protein 1450 mg/24 h
Glucose None
RBCs 70-80/HPF dysmorphic
WBCs 5-8/HPF
Leukocyte Esterase Negative
Nitrites Negative
BUN 35 mg/dL
Creatinine 3.9 mg/dL
Sodium 140 mEq/L
Potassium 5.2 mEq/L
Bicarbonate 15.5 mEq/L
Calcium 9.2 mEq/L
Phosphorus 5.6 mg/dL
Glucose 100 mg/dL
Uric Acid 5.3 mg/dL
C3 & C4 decreased
ANA positive
dsDNA positive
Repeat biopsy shows:

Which of the following is the most appropriate therapy for her current condition?
| A. Mycophenolate and steroid | |
|
|
B. Mycophenolate, tacrolimus and steroids |
| C. Rituximab | |
| D. I.V Immunoglobulins | |
| E. Plasma exchange |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
A 30-year-old man comes to your office for a painful rash on the neck. He has fever and malaise. He has a history of HIV. He is currently taking Tenofovir, emtricitabine, and indinavir. Hise rash is suggestive of herpes zoster:
Physical examination reveals no oral cavity lesions. His cu rent CD4 count is 250/mm3. His chemistry is normal. He is started on an intravenous medication for his rash. Two days later, his chemistry is as follows:
Na 135 mEq/L
K 4.5 mEq/L
CL 100 mEq/L
HCO3 24 mEq/L
BUN 21 mg/dL
Cr 2.0 mEq/L
Glucose 95 mg/dL
Calcium 9.4 mg/dl
Urinalysis shows needle-shaped crystals in the sediment.
Which of the following is most likely the cause of his renal problem?
| A. Indinavir | |
| B. Tumor lysis syndrome | |
| C. Antifreeze ingestion | |
|
|
D. Acyclovir |
| E. IV TMP/SMX |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/17/2026
In patients with CKD and ESRD, Vitamin D appears to protect against cardiovascular events by controlling secondary hyperparathyroidism. The OPERA trial evaluated the effect of the Vitamin D analog paricalcitol in CKD stages 3-5 with left ventricular hypertrophy. The study observed the effect on left ventricular mass and function.
Which of the following statements is true about the effect of paricalcitol in CKD and ESRD patients?
| A. Paricalcitol treatment reduced LV mass | |
| B. Paricalcitol treatment preserved LV ejection fraction | |
| C. Paricalcitol treatment improved pulse wave velocity and arterial stiffness | |
| D. Paricalcitol treatment improved blood pressure control | |
|
|
E. Paricalcitol treatment significantly reduced PTH and alkaline phosphatase |
|
|
Copyright © ABIM Exam World
Created On: 09/20/2017
Last Modified: 10/16/2026
You are rounding on your patients in the dialysis unit and see a 65-year-old gentleman with ESRD due to chronic interstitial disease. He also has a history of diet-controlled diabetes mellitus and hypertension. His other past medical history is significant for dyslipidemia, coronary artery disease, hypothyroidism, gout and depression. He has been hospitalized in the recent past for swelling and pain of his right great toe. He was seen by the foot doctor, a scan was done, and eventually the great toe had to be amputated. He has been on hemodialysis 3 times a week. His weekly Kt/V is 1.9. You are conducting the monthly blood work review for this patient. You note that his hemoglobin has been persistently low for the past few monthly blood draws. He is currently on 100 mcg of Darbepoetin weekly on dial sis. On enquiry, there is no history of blood loss in the form of hematemesis, melena, hematochezia or hemoptysis. His active medication list includes Losartan, Atorvastatin, Calcitriol, multivitamin supplements, paroxetine, allopurinol, aspirin.
His pertinent blood work is as follows:
Test | Result |
WBC | 4500 cells /cumm |
Hemoglobin | 8.2 g/dL |
Platelet count | 450 thousand /cumm |
Reticulocyte count | Normal |
Iron | 55 (range 50-150) |
Total iron-binding capacity | 250 g/dl (range 250-310) |
Transferrin saturation | 20% |
Ferritin | 1400 ng/ml (range 20-235) |
Haptoglobin | 400 mg/dl (range 83-267) |
Lactate dehydrogenase | 240 U/L (range 80-225) |
Total bilirubin | 1.0 mg/dl |
Folate | 7 ng/ml (range 1.8-9.0) |
B12 | 500 pg/ml (range 200-800) |
Peripheral blood smear. | Normal RBC morphology, few burr cells. |
Which of the following is true about this patient’s anemia?
Omitted
|
Correct Answer: Option C: This patient has a chronic inflammatory state that contributes to his anemia.
Explanation:
10-15% of patients receiving erythrocyte-stimulating agents (ESAs) develop resistance. There are multiple reasons why ESRD patients develop resistance.
ESA resistance occurs due to the following reasons:
Iron deficiency.
Chronic inflammation.
Under-dialysis.
Hemolysis.
Folate and B12 deficiency.
Chronic blood loss.
Anti-EPO antibodies.
Pure red cell aplasia.
Failed chronic renal allograft.
ACEI/ARB.
Aluminum overload.
Hyperparathyroidism.
Hematological disorders or malignancy.
Option A: Incorrect option. ESRD is associated with erythropoietin deficiency. The patient is already on ESA. There is no point in measuring EPO levels. There is no evidence that measuring EPO levels is part of the management of anemia in CKD.
Option B: Incorrect option. ESRD is an inflamed state. In an inflammatory milieu, hepcidin production increases. The hepatic iron-regulatory hormone Hepcidin and its receptor, the cellular iron exporter Ferroportin, form a feedback-regulated mechanism that maintains adequate plasma iron-transferrin concentrations for erythropoiesis and other functions, ensures sufficient iron stores, and prevents iron toxicity. In chronic kidney disease, inflammation and impaired renal clearance increase plasma hepcidin, which inhibits duodenal iron absorption and sequesters iron in macrophages. These hepcidin effects can cause systemic iron deficiency, reduced iron availability for erythropoiesis, and resistance to endogenous and exogenous erythropoietin.
Choice C: Correct option. Refer to the explanation for option B. He had pain and swelling of his right great toe; a foot doctor saw him, a bone scan was done and subsequently, amputation. All findings suggest an infective etiology, most likely osteomyelitis. There is a temporal relationship between the patient's anemia and an underlying chronic inflammatory state.
The high ferritin also suggests an inflammatory state.
Choice D: Incorrect option. Pure red cell aplasia, a form of severe ESA hypo-responsiveness mediated by anti-erythropoietin antibodies, was first reported with certain formulations of Epoetin alfa but has now been reported with all commercially available forms of ESA. This syndrome presents with rapid-onset severe anemia (hemoglobin <7 g/dl), severe reticulocytopenia (reticulocyte count <10,000/?l), and marked elevations in serum ferritin (>1000 ng/ml) and transferrin saturation (>70%) due to low iron utilization. Pure red cell aplasia is unlikely given the absence of characteristic laboratory findings. Moreover, the patient did not receive Epoetin alfa.
Choice E: Incorrect option. Under-dialysis leads to anemia due to the same mechanism mentioned earlier in option B. Under-dialysis worsens the uremic milieu, which in turn leads to an inflammatory state. This leads to anemia. The patient in this clinical vignette has been dialysed appropriately. His weekly Kt/V is 1.9, which is above the target goal of 1.7
Copyright © ABIM Exam World
Created On: 10/22/2018
Last Modified: 10/16/2026
50-year-old female patient whose group B is being evaluated for kidney transplant surgery. She had ESRD secondary to analgesic nephropathy and has been on hemodialysis for the last 5 years. She has had multiple sensitization events in the form of 3 pregnancies and several blood transfusions. Her current calculated PRA against class I antigen is 97% and against class II antigen is 99%. She has been enrolled in the national highly sensitized recipient program.
Her husband, who is blood group matched, came forward as a potential kidney donor, but she had a positive Flow B and T-cell crossmatch against him. Single antigen bead assay demonstrates donor-specific antibodies against class I at DQB*15 and DPB*14. This transplant did not materialize as the patient declined the desensitization protocol. Now her younger brother comes forward as a potential donor. He is blood group A, and the flow B and T-cell crossmatch is negative, with no demonstrable donor-specific antibodies against the donor. The patient wants to know more about ABO-incompatible transplant.
Which of the following statements about the ABO incompatible transplant is correct?
| A. Three-year graft survival is inferior to blood group compatible transplants. | |
| B. The infectious and bleeding complications post ABOI kidney transplant are the same as blood matched kidney transplant. | |
|
|
C. All patients undergoing ABOI transplant need to undergo desensitization using IVIg, Plasma exchange, Rituximab irrespective of their donor/recipient pair Anti ABO titers for optimal outcomes. |
|
|
D. C4d staining on protocol biopsies is common feature and does not necessarily mean an antibody mediated rejection process in the absence of allograft dysfunction. |
|
|
Correct answer: Option D: C4d staining on protocol biopsies is a common feature and does not necessarily mean an antibody-mediated rejection process.
Explanation:
Choice A: Three-year graft survival is inferior to blood group-compatible transplants is incorrect. A comprehensive database analysis of 1420 ABOI living donor (LD) kidney transplants performed in 101 centers from 2005 to 2012 compared graft and patient survival with a matched cohort of ABO-compatible transplant recipients. Three-year graft and patient survival were ultimately identical. 1
Choice B: The infectious and bleeding complications post ABOI kidney transplant are the same as in blood-matched kidney transplant is also incorrect. Using USRDS and Medicare data from 2000–2007, 119 ABOI (non-A2 donor) transplant recipients were identified. Compared with ABO-compatible recipients, the risks of infectious and hemorrhagic complications were significantly higher, with a 2.2-fold higher risk of pneumonia, a 3.5-fold higher risk of wound infections, a 56% higher risk of pyelonephritis, and a nearly 2- fold higher risk of hemorrhage 2
Choice C: All patients undergoing ABOI transplant need to undergo desensitization using IVIg, Plasma exchange, Rituximab irrespective of their donor/recipient pair. Anti-ABO titers for optimal outcomes is also an incorrect answer. Historically, ABOI transplantation has been successful when performed after desensitization with plasmapheresis, intravenous Ig (IVIG), rituximab, and/or splenectomy to achieve ABO IgG antibody titersof 1:4. A recent publication demonstrated that these intensified treatments might not be necessary in donor/recipient pairs who have low-to-moderate titer ABO incompatibility 3
Choice D: C4d staining on protocol biopsies is a common feature and does not necessarily mean an antibody-mediated rejection process; in the absence of allograft dysfunction, this is the correct answer. C4d staining is not an uncommon feature seen in the protocol biopsies done in ABOI kidney transplant recipients. In the absence of allograft dysfunction, C4d staining has no clinical relevance and is part of graft accommodation.
Copyright © ABIM Exam World
Created On: 10/30/2018
Last Modified: 10/16/2026
A 28-year-old Caucasian gentleman comes to the clinic for a follow-up visit. He has been found to have type 1 diabetes mellitus since the age of 12 years. His cousin has the same disease. He reports no symptoms. He uses an insulin pump with insulin aspart. He monitors blood sugar with a flash glucose monitor and uses carbohydrate counting; he reports infrequent hypoglycemic episodes, particularly 2 hours post-lunch, which he manages himself. He exercises at least 60 minutes per day. His vitals recordishow118/6 mmHg. His BMI is 23.2. System examination is unremarkable.
His laboratory investigations are reported as follows.
Characteristic | Value |
Hemoglobin | 14.2 gm/L |
WBC count | 6.8 X 10³/cubic mm |
Platelet count | 241 X 103/cubic mm |
Segmented Neutrophils Lymphocytes Monocytes Band neutrophils Eosinophils Basophils | 60% 36% 2% 0% 2% 0% |
Sr Sodium | 139 mEq/L |
Sr Potassium | 4.4 mEq/L |
Sr Creatinine | 0.6 mg/dL |
eGFR using CKD-EPI | 136.8 ml/min/1.73m2 |
Sr Bicarbonate | 24 mEq/L |
Sr Chloride | 101 mEq/L |
Total Bilirubin | 1.0 mg /dL |
AST | 16 U/L |
ALT | 18 U/L |
Sr Albumin | 4.0 g/dL |
HBA1C | 7.9% |
Sr Calcium | 10 mg/dL |
Urine dipstick | pH- 5.4 Albumin-nil no blood no WBCs |
24-hour urinary protein | 76 milligrams/day |
What is the MOST LIKELY incorrect statement regarding the hyperfiltration stage of Diabetic Kidney Disease in this patient?
| A. Renal hyperfiltration is usually diagnosed when the GFR is more than 120 ml/min,which corresponds to a renal function that exceeds two standard deviation above mean GFR. | |
| B. Renal hyper filtration usually precedes microalbuminuria in type 1 diabetes mellitus. | |
|
|
C. Renal hyper filtration is considered as a risk factor for future progression to chronic kidney disease (CKD) and end stage renal disease (ESRD) in type 1 DM. |
|
|
D. eGFR equations like MDRD equation can be used predict hyper filtration. |
|
|
The Correct Answer is Option D: eGFR equations like the MDRD equation can be used pto redict hhyperfiltration
Explanation:
Supraphysiological elevation in GFR is observed early in the natural history of type 1 and type 2 diabetes mellitus, due to glomerular hyperfiltration. The pathogenesis of hyperfiltration in diabetes is complex, with a prominent role for hyperglycemia and altered insulin levels, especially in early diabetes and pre-diabetes. Dilatation of the afferent (pre-capillary) glomerular arteriole plays an important role in the hyperfiltration response by raising both intra-glomerular pressure and renal blood flow.
Direct measurement of GFR is usually required to detect hyperfiltration because estimation equations, such as the Modification of Diet in Renal Disease (MDRD), usually underestimate the true GFR when it is normal or above normal.
Option A: A definite cGFR cutoff is lacking. However, renal hyperfiltration is typically defined as a GFR between 120 mL/min and 150 mL/min/1.73 m2, or greater than 2 standard deviations above the mean GFR in normal, healthy individuals.
Option B: Hyperfiltration in diabetes precedes the onset of albuminuria and/or decline in renal function, and predisposes to progressive nephron damage by increasing glomerular hydraulic pressure
Option C: Hyperfiltration alone does not seem to fully explain adverse renal outcomes, as the risk for ESRD in transplant donors is very low. However, in type 1 diabetes, rapid GFR decline is associated with renal hyperfiltration and impaired GFR and may predict progressive DKD before loss of renal function.
Copyright © ABIM Exam World
Created On: 10/30/2018
Last Modified: 10/16/2026
A 19-year-old African American woman comes to the clinic for a follow-up visit. She has been found to have type 1 diabetes mellitus since the age of 12. She has been using an insulin pump for the last 5 years. She reports no hypoglycemic symptoms and has been monitoring blood sugar with a flash glucose monitor. She reports infrequent hypoglycemic episodes, all of which are self-managed. She met with an ophthalmologist for eye screening and has no retinopathy. She exercises regularly for 30 mins. Her vitals show BP 127/66 mmHg. Her BMI is 22.2. Systemic examination is unremarkable.
Her laboratory investigations are as follows.
Characteristic | value |
Hemoglobin | 13.2 gm/L |
WBC count | 7.8 X 10³/cubic mm |
Platelet count | 241 X 103/cubic mm |
Segmented Neutrophils Lymphocytes Monocytes Band neutrophils Eosinophils Basophils | 60% 36% 2% 0% 2% 0% |
Sr. Sodium | 136 mEq/L |
Sr. Potassium | 4.2 mEq/L |
Sr. Creatinine | 0.6 mg/dL |
eGFR using CKD-EPI | 153.1 ml/min/1.73m2 |
Sr. Bicarbonate | 24 mEq/L |
Sr. Chloride | 101 mEq/L |
Total Bilirubin | 1.0 mg /dL |
AST | 16 U/L |
ALT | 18 U/L |
Sr. Albumin | 4.0 g/dL |
HBA1C | 8.2% |
Sr. Calcium | 10 mg/dL |
Urine dipstick | pH- 5.4 Albumin-nil no blood no WBCs |
24-hour urinary protein | 86 milligrams/day |
What is the MOST LIKELY False statement regarding the renal hyperfiltration stage of Diabetic Kidney Disease in this patient?
| A. Renal hyper filtration is attenuated by SGLT2 inhibition. | |
| B. Renal hyper filtration occurs in both type 1 and type 2 diabetes mellitus. | |
| C. Obesity can also lead to single-nephron hyper filtration. | |
|
|
D. Incretins like GLP-1 and GIP are neutral in terms of altering renal hemodynamics unlike SGLT2 blockers. |
|
|
The Correct Answer is Option D: Incretins like GLP-1 and GIP do not alter renal hemodynamics, unlike SGLT2 blockers.
Supraphysiologic elevation in GFR occurs early in the natural history of type 1 and type 2 diabetes mellitus due to glomerular hyperfiltration. Pathogenesis of hyperfiltration in diabetes is complex, with a prominent role for hyperglycemia and distorted insulin levels, especially in early diabetes and pre-diabetes. Dilatation of the afferent (pre-capillary) glomerular arteriole plays an important role in the hyperfiltration response, by raising both the intra-glomerular pressure and renal blood flow.
The effects of incretins can be demonstrated experimentally using GLP-1 receptor agonists (GLP-1RAs) and dipeptidyl peptidase (DPP) -4 inhibitors, which have renal hemodynamic effects beyond glycemic control. These observations are attributed to GLP-1–mediated inhibition of NHE3 (also associated with DPP-4 inhibition) in the proximal tubular brush border, reducing proximal sodium reabsorption and activating TGF (tubuloglomerular feedback).
Option A: In an 8-week study, empagliflozin in T1DM patients with whole-kidney hyperfiltration (mean GFR 172±23 ml/min per 1.73 m2) demonstrated a glucose-independent 19%decrease in GFR, which was associated with a decline in ERPF (estimated renal plasma flow) and estimated glomerular pressure and an increase in afferent arteriolar resistance, as assessed by the Gomez equations. SGLT2 inhibition could reduce (single-nephron) hyperfiltration in diabetes by restoring sodium-chloride concentration at the macula densa and subsequent TGF-mediated afferent arteriolar vasoconstriction.
Option B: Reported prevalence of hyperfiltration at the whole-kidney level varies greatly: between 10% and 67% in type 1 diabetes mellitus (T1DM) (with GFR values up to 162 ml/min per 1.73 m2), and 6%–73% in patients with type 2 diabetes (T2DM) (up to 166 ml/min per 1.73 sq. m.
Independent of diabetes and glucose levels, body weight also augments GFR (by about 15% in obese subjects to about 56% in severely obese non-diabetic subjects).
Copyright © ABIM Exam World
Created On: 10/31/2018
Last Modified: 10/16/2026
A 68-year-old Caucasian gentleman comes to the clinic for a follow-up visit. He is known to
have type 2 diabetes mellitus for the past 18 years. His father had diabetes from age 40 and developed kidney disease requiring dialysis after 15 years
of diabetes. He reports no symptoms. He has had hypertension and
coronary artery disease with a history of PCI 2 years ago. He has
non-proliferative diabetic retinopathy. His medications are sitagliptin,
gliclazide and metformin, in addition to losartan and hydrochlorothiazide. He
monitors blood sugar at home and reports no hypoglycemia. He
exercises at least 30 minutes per day. His vitals recording shows BP
of 68/66 mm Hg. His BMI is 29.2. Systemic examination is unremarkable.
His laboratory investigations are as follows.
Characteristic | value |
Hemoglobin | 12.2 gm/L |
WBC count | 6.8 X 10³/cubic mm |
Platelet count | 241 X 103/cubic mm |
Segmented Neutrophils Lymphocytes Monocytes Band neutrophils Eosinophils Basophils | 60% 36% 2% 0% 2% 0% |
Sr. Sodium | 139 mEq/L |
Sr. Potassium | 4.9 mEq/L |
Sr. Creatinine | 1.2 mg/dL |
Sr. Bicarbonate | 22 mEq/L |
Sr. Chloride | 101 mEq/L |
Total Bilirubin | 1.0 mg /dL |
AST | 16 U/L |
ALT | 18 U/L |
Sr. Albumin | 4.0 g/dL |
HBA1C | 7.8% |
Sr. Calcium | 10 mg/dL |
Urine dipstick | pH- 5.4 Albumin-trace no blood no WBCs |
24-hour urinary albumin | 200 milligrams/day |
What is the MOST LIKELY correct statement regarding the clinical diagnosis of Diabetic Kidney Disease in this patient?
|
|
A. Diabetic Kidney Disease previously called as diabetic nephropathy can be diagnosed clinically with renal biopsy only. |
| B. Presence of microalbuminuria is adequate for clinical diagnosis of Diabetic Kidney Disease. | |
| C. Presence of hematuria without non-diabetic kidney disease is impossible in Diabetic Kidney Disease as diabetic kidney disease is a non-proliferative glomerular disease. | |
|
|
D. Family history of Diabetic Kidney Disease is associated with renal involvement in Diabetes. |
|
|
The Correct Answer is
Option D: Family history of Diabetic Kidney Disease is associated with renal
involvement in Diabetes.
Familial studies have demonstrated clustering of diabetic nephropathy. Patients with DM who have a first-degree relative with T1/T2DM and diabetic nephropathy have a higher risk of developing diabetic nephropathy than those without an affected relative. This familial clustering has also been well documented in the Pima Indian populCandidatendidateincludeied are glucose transp orter 2(GLUT2), transforming growth factor beta (TGF-?), and endothelial nitric oxide synthase (eNOS).
Option A: Diabetic nephropathy is a clinical syndrome characterized by the following:
·
Persistent
albuminuria (>300 mg/d) that is confirmed on at least 2 occasions 3-6 months
apart
·
Progressive
decline in the glomerular filtration rate (GFR)
·
Elevated
arterial blood pressure
Option C: Microhematuria has been demonstrated in biopsy studies with isolated diabetic nephropathy. Red blood cell casts have also been described in patients with diabetic nephropathy. However, it is important to rule out other glomerular and extra-glomerular causes of hematuria.
Copyright © ABIM Exam World
Created On: 10/31/2018
Last Modified: 10/16/2026
A 30-year-old man was on hemodialysis for 6 months. He was an IV drug user and was diagnosed with HIV. His elder sister came forward as a potential kidney donor for him. He underwent a successful kidney transplant. Which of the following statements is true regarding kidney transplantation in HIV positive individuals and acute rejection episodes?
|
|
A. The episodes of acute rejection are more in HIV positive individuals compared to non-HIV positive patients. |
| B. The episodes of acute rejection are same in HIV positive individuals when compared to age and disease matched non-HIV counterparts. | |
| C. Cyclosporine is a preferred CNI as it has some invitro antiviral properties. | |
| D. There is a documented interaction between CNI and integrase inhibitors. Integrase inhibitors increase the CNI level. | |
| E. There is a proven benefit of using rATG for induction immunosuppression over anti IL-2 therapy to prevent rejections. |
|
|
Correct Answer. Option A. The episodes of acute rejection are more common in HIV positive individuals compared to non-HIV-positive patients.
Explanation.
Kidney transplant recipients with HIV have a high frequency of rejection. In a large, multicenter trial, one- and three-year rejection rates were 31% and 41%, respectively, compared with an expected one-year rejection rate of 12%, as reported by SRTR for all kidney transplant recipients. At European transplant centers, where most patients are induced with interleukin (IL)-2 receptor antibodies, one-year acute rejection rates among recipients with HIV have ranged from 15 to 44 %.
The higher rate of rejection in recipients with HIV is likely multifactorial. Drug-drug interactions between calcineurin inhibitors (CNIs) and protease inhibitors (PIs) can lead to subtherapeutic exposure to immunosuppressive agents. Patients on a CNI and PI require nonstandard dosing schedules (i.e., every other or every third day), which can make adherence difficult. Furthermore, concomitant administration of a PI and CNI results in a 40 % lower area under the curve (AUC) for CNI exposure at the same CNI target level, leading clinicians to underdose patients taking both medications systematically. Many transplant physicians seek to transition patients off PI-based regimens whenever possible in favor of integrase inhibitor-based regimens, which avoid these drug-drug interactions and permit standard immunosuppression dosing.
HIV-infected transplant recipients, compared with HIV-negative recipients, have a higher risk of acute rejection and, therefore, would theoretically benefit from antibody induction therapy. However, given the underlying immunosuppressed state of HIV-infected patients, prolonged lymphocyte depletion with antibody induction therapy could potentially increase their risk of developing opportunistic infections. Some centers avoid the use of antibody induction therapy among HIV-infected transplant recipients. In centers that use antibody induction therapy, some use basiliximab (an IL-2 receptor antibody) based on data from two studies of HIV-infected kidney transplant recipients that demonstrated an increased risk of infection among those treated with rATG-Thymoglobulin. Other centers prefer to use rATG-Thymoglobulin given its superior efficacy in preventing acute rejection in HIV-negative recipients.
Copyright © ABIM Exam World
Created On: 05/12/2020
Last Modified: 10/12/2026
A 45-year-old female is waitlisted for a kidney transplant. Her native kidney disease is IgA nephropathy. Her blood group is B, and her CPRA is 90%. You are seeing her in the clinic as part of kidney transplant work. As part of documentation, you discuss with her the Public Health Service – Increased Risk Donors (PHS-IRD). You explain PHS-IRD and ask whether she consents. Your rationale for explaining this is the long wait time for blood group B in your allocation area, especially under CPRA 90%. Which of the following statements regarding the PHS-IRD is TRUE?
| A. As per the new guidelines there is no need to take an informed consent for PHS-IRD from the potential recipient. | |
|
|
B. PHS-IRD kidneys have a discard rate of 2.5-fold. |
| C. The kidney from PHS-IRD have an infection transmission risk anywhere between 10-15% depending on the type of infection. | |
| D. Recipient who received IRD kidneys have increased risk of death at 6 months compared to those who declined the offer. | |
|
|
E. There is increased risk of allograft loss in recipients of PHS-IRD kidneys. |
|
|
Correct Answer. Option B. PHS-IRD kidneys have a discard rate of 2.5-fold.
Explanation.
The United States Public Health Service (PHS) redefined donors who were previously classified by the Centers for Disease Control and Prevention as being at increased risk for transmission of hepatitis B virus (HBV), hepatitis C virus (HCV), and HIV. The number of deceased donors that are part of this classification has increased dramatically because of the opioid epidemic, comprising over 20% of donor kidneys. Overall, overdose-death donors accounted for 1.1% of organ donors in 2000 and 13.4% in 2017. Importantly, transplantation candidates and providers should be well versed in the very low risk of disease transmission from these donors, all significantly < 1% even under the highest-risk circumstances (intravenous drug overdose, syringe-on-person). Unfortunately, “PHS increased-risk donor” (IRD) status is independently associated with nearly 2.5-fold increased odds of turndown. An analysis by Bowring et al. used SRTR data from 104,998 kidney transplantation candidates who were offered IRD kidneys that were eventually accepted. The median KDPI of these kidneys was 30 (interquartile range, 16–49). Importantly, after 5 years, only 31.0% of candidates who declined IRDs received non-IRD DDKTs later; the median KDPI of these non-IRD kidneys was 52. Those who accepted an IRD had a substantially lower risk of death at 1 to 6 months after decision (aHR, 0.50; 95% CI, 0.67 to 0.90; P=0.006) and beyond 6 months after decision (aHR, 0.46; 95% CI, 0.52 to 0.58; P< 0.001). A single-center report of PHS-IRD kidney utilization reviewed offers made to 2423 kidney transplant candidates from June 2004 to May 2005; 1502 ultimately received a transplant with or without a PHS-IRD kidney. Accepting a PHS-IRD kidney offer was associated with lower mortality (3.63% versus 11.6%; aHR, 0.467; P = 0.0008) and a lower risk of allograft loss than in non–PHS–IRD recipients (P = 0.007), with no transmission of HCV, HBV, or HIV.

Copyright © ABIM Exam World
Created On: 05/12/2020
Last Modified: 10/12/2026
All the drugs mentioned below cause hyperkalemia. All the drugs act by a specific mechanism to induce hyperkalemia. Only one drug acts through a different mechanism. Which drug induces hyperkalemia via a different mechanism than the others?
|
|
A. Heparin. |
| B. Low molecular weight heparin. | |
| C. Aminoglutethimide. | |
| D. Dabigatran. | |
|
|
E. Calcineurin inhibitors. |
|
|
Correct Answer. Option D. Calcineurin inhibitors.
Explanation.
Heparin, low-molecular-weight heparin, Aminoglutethimide and Dabigatran all impair adrenal hormone metabolism. These drugs cause potent inhibition of adrenal hormone synthesis, leading to hyperkalemia.
The hyperkalemia seen with calcineurin inhibition is likely multifactorial and relates to inhibitory effects on Na+-K+-ATPase in collecting ducts and possibly to distal tubular acidosis. In addition, there is evidence that decreased numbers of mineralocorticoid receptors, which are detected in 75% of patients who are treated with cyclosporine, lead to hyperkalemia and metabolic acidosis as a result of aldosterone resistance. Recently, it was demonstrated that cyclosporine reduces paracellin-1 expression in thick ascending limb cells. This decrease in magnesium transport likely contributes to the magnesium wasting and hypomagnesemia induced by cyclosporine, which is associated with chronic interstitial fibrosis, faster declining kidney function, and increased rates of graft loss in renal transplant recipients with CNI nephrotoxicity. Finally, it was shown that cyclosporine indirectly opens ATP-sensitive K+ channels by inhibiting calcineurin, which could contribute to the CNI-associated hyperkalemia.
Copyright © ABIM Exam World
Created On: 05/18/2020
Last Modified: 10/12/2026
A 25-year-old man is referred to you for evaluation of nephrotic syndrome. A kidney biopsy is done, and it shows minimal change disease. His BP is 150/90 mmHg, and his heart rate is 70 bpm. His current medications are prednisone 40 mg once daily, furosemide 40 mg twice daily, Ramipril 10 mg once daily, and Calcium + vitamin D supplementation. Clinical exam shows raised JVD 3 + pitting edema to the right thigh. His blood work shows serum creatinine 0.9 mg/dL, BUN 35 mg/dL, and serum potassium 3.2 mEq/L. Urine analysis is bland, and his 24 hr urine protein is 5.8g. He is strictly following his salt restriction. After a month’s follow-up, his proteinuria has decreased to 4.0 g/24 hrs, but his foot edema remains unchanged. His Sr albumin has improved from 1.9 g/L to 2.8 g/L. Which of the following drugs will benefit the patient?
| A. Metolazone. | |
| B. Amiloride. | |
| C. Chlorthalidone. | |
| D. Cyclophosphamide. | |
| E. Amlodipine. | |
| F. Losartan. |
|
|
Correct Answer. Option B. Amiloride.
Explanation.
Two major factors, both of which lead to retention, have been thought to be responsible for the development of edema in patients with nephrotic syndrome; both likely contribute to a variable degree in individual patients:
Distinguishing between these mechanisms is clinically important because it affects tolerance of diuretic therapy. Diuretics are well tolerated in patients with renal sodium retention but, if underfilling is the primary mechanism, can lead to worsening hypovolemia as evidenced clinically by an elevation in serum creatinine.
Studies in experimental animals with unilateral nephrotic syndrome or glomerulonephritis suggest that primary sodium retention in these disorders is due to increased sodium reabsorption in the collecting tubules, which is also the site of action of atrial natriuretic peptide (ANP) and the related renal hormone urodilatin. This is called the overfill hypothesis because primary renal sodium retention leads to volume expansion.
Increased activity of the epithelial sodium channel (ENaC) may contribute to sodium retention. Serine proteases are aberrantly filtered in nephrotic syndrome, increasing their concentration in the urine. Plasminogen (which is activated by epithelial urokinase-type plasminogen activator [uPA] to plasmin) in nephrotic urine may activate ENaC via proteolytic cleavage of the gamma chain, providing a potential mechanism by which filtered proteins cause sodium retention. It also explains the observation that remission from the nephrotic syndrome is generally preceded by a decrease in urinary protein excretion. In an animal model of nephrotic syndrome, mice treated with the serine protease inhibitor aprotinin normalized urinary serine protease activity and prevented sodium retention. A similar result was seen when rats with nephrosis were treated with the ENaC inhibitor amiloride.
Hence, amiloride is the best answer for this clinical vignette.
Copyright © ABIM Exam World
Created On: 05/18/2020
Last Modified: 10/12/2026
A 68-year-old Hispanic woman is referred to you for evaluation of nephrotic syndrome. She has a history of type 2 diabetes and hypertension. Both diabetes and hypertension are well controlled. Her serum creatinine is 2.1 mg/dL. Urinalysis shows only proteinuria, with a protein-to-creatinine ratio of 6. A renal biopsy shows amyloidosis and interstitial fibrosis. Based on the history, biopsy findings, and proteinuria above, which diagnostic test would you order to characterize the type of her amyloidosis?
| A. Electron microscopy of the glomerulus. | |
| B. Immunofluorescent studies. | |
| C. Immunofixation study. | |
|
|
D. Amyloidosis derived from leukocyte chemotactic factor 2 (ALECT 2). |
| E. No further testing. |
|
|
Correct Answer. Option D. Amyloidosis derived from leukocyte chemotactic factor 2 (ALECT2).
Explanation.
ALECT2 amyloidosis is a systemic form of amyloidosis with predominantly renal and liver involvement. Most reported cases in North America (88 to 92 %) occur in older Hispanic adults of Mexican origin. However, Punjabis, First Nations people in British Columbia, and Native Americans also have a predisposition for this disorder. In one study of renal amyloidosis among Egyptians, ALECT2 amyloidosis was the second most common form of renal amyloidosis behind AA and ahead of AL amyloidosis. Cases have also been reported in Pakistani, Sudanese, and Chinese patients. The pathogenesis of ALECT2 amyloidosis remains poorly understood. Patients typically present with chronic kidney disease (CKD) and variable proteinuria; nephrotic syndrome is uncommon. Diagnosis requires a kidney biopsy, preferably with laser microdissection and mass spectrometry. Patients with ALECT2 amyloidosis characteristically have diffuse Congo red-positive amyloid deposition in the cortical interstitium, with variable glomerular and vascular involvement. Overall, patients with ALECT2 amyloidosis have better survival than those with AL or AA amyloidosis, possibly because cardiac involvement is absent or rare. However, renal survival is relatively poor, with up to 39 percent of patients progressing to end-stage renal disease (ESRD). There are no specific therapies for ALECT2 amyloidosis.
Copyright © ABIM Exam World
Created On: 05/19/2020
Last Modified: 10/12/2026
A 50-year-old male is referred for evaluation of high-grade proteinuria. He does not have diabetes but is known to have hypertension. He takes hydrochlorothiazide 12.5 mg once daily for that. The blood and urine tests are shown below. You perform a kidney biopsy, and it shows focal segmental glomerulosclerosis (FSGS). The concern is whether this is primary vs. secondary FSGS. Which of the following options would be supportive of secondary FSGS as opposed to primary FSGS?
Value | Test |
11.2 gm/L. | Hemoglobin |
6,800 cells/cumm | WBC count |
2,41,000 cells/cumm | Platelet count |
139 mEq/L. | Sr. Sodium |
5.2 mEq/L. | Sr. Potassium |
1.6 mg/dL. | Sr. creatinine |
22 mEq/L. | Sr. Bicarbonate |
101 mEq/L. | Sr. Chloride |
4.0 g/dL. | Sr. Albumin |
10 mg/dL. | Sr. Calcium |
p: 5.4. Albumin-++++ No blood. No WBCs. | Urine |
3.8 grams/day.
| 24-hour urinary protein |
Negative
| ANCA |
Negative
| ANA |
No monoclonal proteins | Serum protein electrophoresis |
negative | HIV |
negative | HbsAg |
negative | Anti HCV |
| A. Increase in mesangial matrix. | |
| B. Focal sclerosis only in some parts of the glomerulus in primary FSGS. | |
|
|
C. Serum albumin and width of foot processes (effacement of foot processes). |
| D. Tram-tract appearance of the basement membrane. |
|
|
Correct Answer. Option C. Serum albumin and width of foot processes (effacement of foot processes).
Explanation.
The causes of FSGS may be primary (idiopathic) or secondary. Secondary forms are generally characterized by glomerular hyperfiltration and hypertrophy. It was suggested that serum albumin and the degree of foot processes effacement can distinguish primary from secondary forms of FSGS. Praga et al. reported that serum albumin levels are <3 g/dL in those with biopsy-proven primary FSGS, compared to
>3.5 g/dL in those patients with secondary FSGS. A histopathologic study by Deegens et al. showed that foot process width is significantly higher (3200 nm) in primary FSGS than in secondary FSGS (1098 nm; normal 562 nm). Overall, foot process width over 1500 nm differentiated idiopathic from secondary FSGS with high sensitivity and specificity. This suggests that patients with primary FSGS have complete effacement of foot processes, whereas secondary FSGS shows patchy effacement.
In a study of 46 patients with an FSGS lesion, patients were divided by the degree of foot process effacement observed on kidney biopsy. Patients were categorized as having diffuse (?80 %) or limited (<80 %) foot process effacement. Compared with patients with limited foot process effacement, those with diffuse foot process effacement without an identifiable cause had lower serum albumin levels, higher proteinuria and were more likely to have nephrotic syndrome at presentation (100 vs 4 %). Based upon these results, patients who presented with diffuse foot process effacement without an identifiable cause and nephrotic syndrome were classified as primary FSGS. Patients with segmental foot process effacement, with or without an identifiable cause, or diffuse foot process effacement due to an identifiable cause were classified as secondary FSGS.
Copyright © ABIM Exam World
Created On: 05/19/2020
Last Modified: 10/12/2026
All of the following help predict AV Graft stenosis EXCEPT:
| A. Hyperpulsatility of the AV Graft | |
| B. Reduced pulse augmentation | |
| C. Increased bleeding and clots | |
| D. Decreased KT/V | |
| E. Decreased Blood Flow rate | |
|
|
F. Surveillance of the graft |
|
|
Copyright © ABIM Exam World
Created On: 09/23/2020
Last Modified: 10/12/2026
Do you want to end this review?